A concussion is a brain injury from a hit or a sudden jolt, and it often feels like a headache with a dull, slowed-down head. A CT scan usually looks normal. Go to the emergency room now for vomiting more than once, a worsening headache, weakness on one side or trouble staying awake.
What is a concussion?
A concussion is an injury to how the brain works, caused by a force that moves the brain inside the skull. The force can come straight to the head, or through the body, as in a fall. The brain’s structure stays intact, so a CT scan, the X-ray based scan used after a head injury, usually looks normal.
That is why a doctor makes the diagnosis by examining you and asking about the injury. Doctors also call it a mild traumatic brain injury, which is the term you will see on a chart or a referral slip.
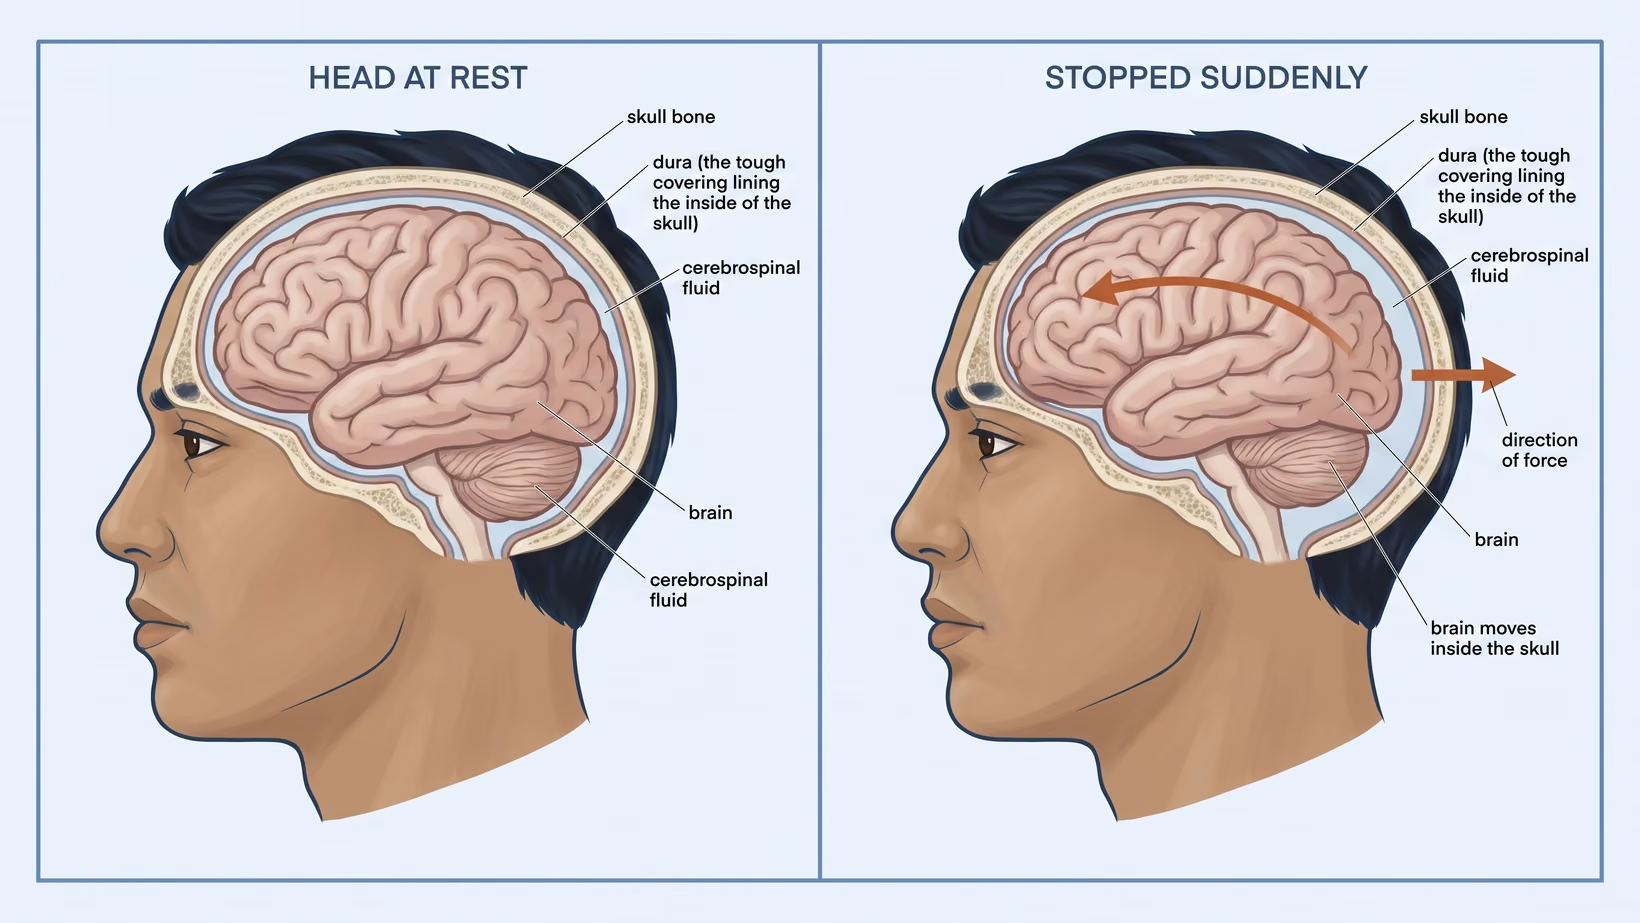
A concussion happens at every age. In babies, children and teenagers, a head injury is checked by a different set of rules.
What does a concussion feel like in the first hours and days?
A concussion usually feels like a headache with a dull, slowed-down head. It is hard to think clearly or hold a conversation, and light and noise are unpleasant. There is no single symptom that every person gets. Some symptoms start right away, and some only appear later the same day.
Symptoms that start right away
- Headache, or pressure in the head
- Feeling dazed, slowed or not quite yourself
- Dizziness, or the room moving
- Nausea, or vomiting once
- Blurred or doubled vision
- A gap in memory around the moment of the injury
- Ringing in the ears
Symptoms that only appear later the same day
- Trouble concentrating, or losing the thread of a task
- Sleeping much more than usual, or not sleeping (a person who is hard to wake, or will not stay awake, needs the emergency room now)
- Being irritable, tearful or flat
- Light and noise feeling painful
- Feeling off balance when standing up
A symptom from this list that starts later in the day is common. On its own, it is not a danger sign. Go to the emergency room now if symptoms are getting worse, or for any danger sign below, whenever it starts.
Can you have a concussion without losing consciousness?
Yes, you can have a concussion without losing consciousness. Many people stay awake throughout and still have one. Doctors diagnose a concussion from how the brain is working after the injury, and blacking out is not needed for the diagnosis. The symptoms are real whether or not you blacked out.
If you stayed awake, the doctor may be less worried about bleeding inside the skull. It does not mean the injury is nothing. Any danger sign below still means the emergency room now.
What does loss of consciousness after head trauma mean?
Losing consciousness after head trauma means the force was enough to stop normal brain function for a moment. It makes bleeding inside the skull more likely, but on its own it does not tell you whether there is a bleed.
In a 2024 review of 17 studies of adults who reached an emergency department awake after a head injury, a bleed was more likely in people who had lost consciousness than in people who had not. The strongest warning sign was a sign of a fracture at the base of the skull: blood behind the eardrum, bruising around both eyes or behind the ear, or clear fluid leaking from the nose or ear.
Headache and being drunk did not predict a bleed in that review, but neither rules one out. A headache that keeps getting worse is a danger sign. A person who is drunk after a head injury should be checked in the emergency room the same day for a bleed on the brain.
Seek care now
Danger signs in the first 48 hours: go to the emergency room now
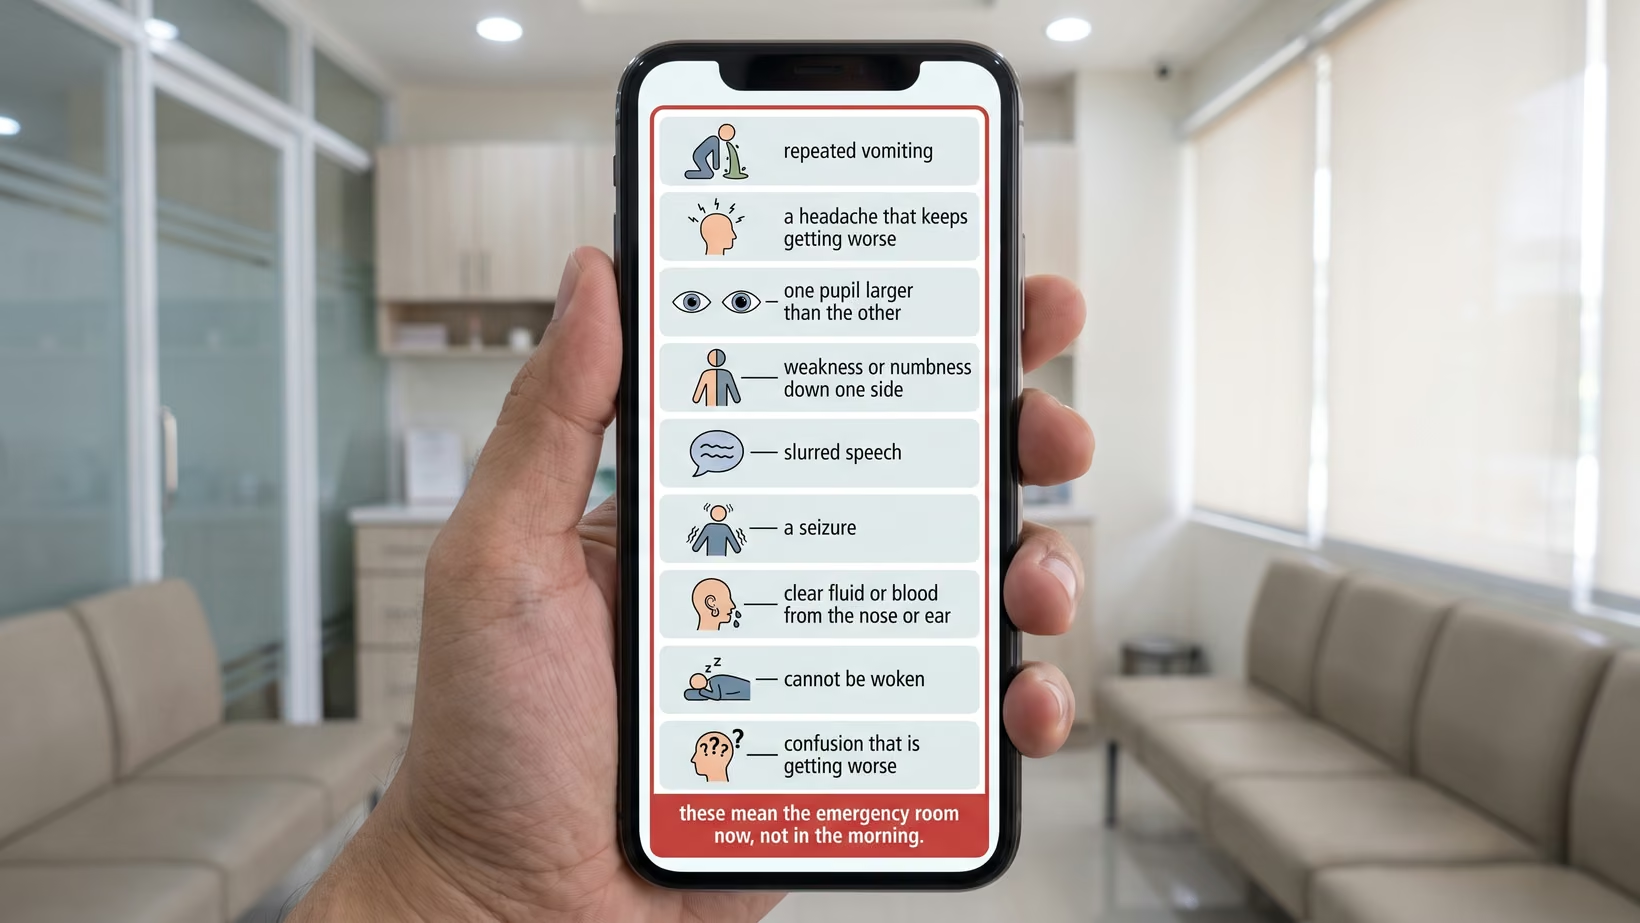
Go to the emergency room now, not in the morning, for any one of these signs in the first 48 hours after a head injury. One sign is enough.
- Vomiting more than once
- A headache that keeps getting worse instead of settling
- One pupil larger than the other
- Weakness, numbness or clumsiness down one side
- Slurred or confused speech
- A seizure, or any jerking that cannot be stopped
- Clear fluid or blood coming from the nose or the ear
- Cannot be woken, or will not stay awake
- Confusion or restlessness that is getting worse over hours
A relative can see each of these signs without any equipment. In a baby or young child who cannot talk or walk, these signs are hard to see. If a baby or young child is not acting like themselves after a head injury, go to the emergency room now.
What to do now
What to do now: on the way to the emergency room, or if symptoms do not settle
If the person is drowsy or has vomited, keep them still and lying on their side. This is the first step of what to do before you reach the emergency room. Do not give food, drink or a painkiller until a doctor has seen them. Do not let them drive themselves. Tell the doctor which regular medicines they take.
Write down the time of the injury and the time each symptom started. If they lost consciousness, write down how long. This record changes what the doctor does next.
If there is no danger sign but symptoms are not settling after a few weeks, you can come to me.
I see adults at my clinic at the Lung Center of the Philippines, Room 1101, Quezon Avenue, Quezon City, on Tuesday and Thursday from 2 PM. I see children at my clinic at PCMC, Room 22, Quezon Avenue corner Agham Road, Diliman, Quezon City, on Wednesday from 2 PM.
Book a consultation with me, or ask your doctor to refer you to me. If you live too far to come to Quezon City, you can book an online consult on the consultation page.
Bring and ask
What to bring to the emergency room, and what to tell the doctor
- A list of every medicine taken, especially a blood thinner (an anticoagulant or antiplatelet medicine, which makes the blood slower to clot)
- Any previous brain scan or brain operation record
- The time of the injury and what exactly happened
- Whether consciousness was lost, and for how long
- What the person cannot remember, and from when to when
- Whether there was alcohol, and roughly how much
- The name of someone who saw it happen
Concussion treatment at home: what actually helps
Concussion treatment at home starts with a short period of reduced activity, and light activity such as walking can begin in the first two days. Lying in a dark room until every symptom has gone does not make recovery faster. In studies of sport concussion, early light activity and gentle aerobic exercise set by a clinician shortened recovery by about four to five days. Cutting down screen time in the first two days also helped.
Those studies were mostly in people with a concussion from sport. They do not show whether the same advice applies to an older adult after a fall, or to anyone with a bleed on the scan.
Someone responsible should stay with the person for the first 24 hours and be able to wake them. Sleep is allowed. Keep the room quiet and the light low, and avoid screens where possible. Take short walks instead of staying in bed all day. While you are dizzy or unsteady, walk with someone beside you.
Add one activity at a time, and stop when symptoms clearly increase. Poor sleep after a concussion is linked to slower recovery, so keep a regular bedtime as part of the treatment.
What not to do after a concussion
After a concussion, do not go back to contact sport, riding a motorcycle, climbing or any activity where a second hit is possible while symptoms remain. Being drunk hides the signs everyone is watching for, so do not drink alcohol in the first days. Do not drive while you are dizzy, slowed or having trouble concentrating.
Do not rely on feeling fine. The standard written advice after a head injury says that some people seem to recover quickly and then have difficulty or complications later.
If the scan was normal and the symptoms are now getting worse, go back to the emergency room now. Do not wait for morning for any danger sign.
Paracetamol or ibuprofen after a concussion: which is safer?
We found no guideline that says paracetamol is safer than ibuprofen after a concussion, or the other way around. Ask the doctor who saw the injury which one is safer for you. Ask them to write down which medicine, how much and how often, for your situation.
Ask before you take either if you are on a blood thinner, if a scan showed any bleeding, if you have a stomach ulcer or kidney problem, or if you are pregnant. If you cannot reach that doctor, a pharmacist can answer the general question.
How long does a concussion last, and when can you return to work, school or sport?
Most people with a concussion improve over time, and some take longer than others. No reliable figure covers all ages. The figures from sport and from children do not describe how long a concussion lasts in an older adult after a fall.
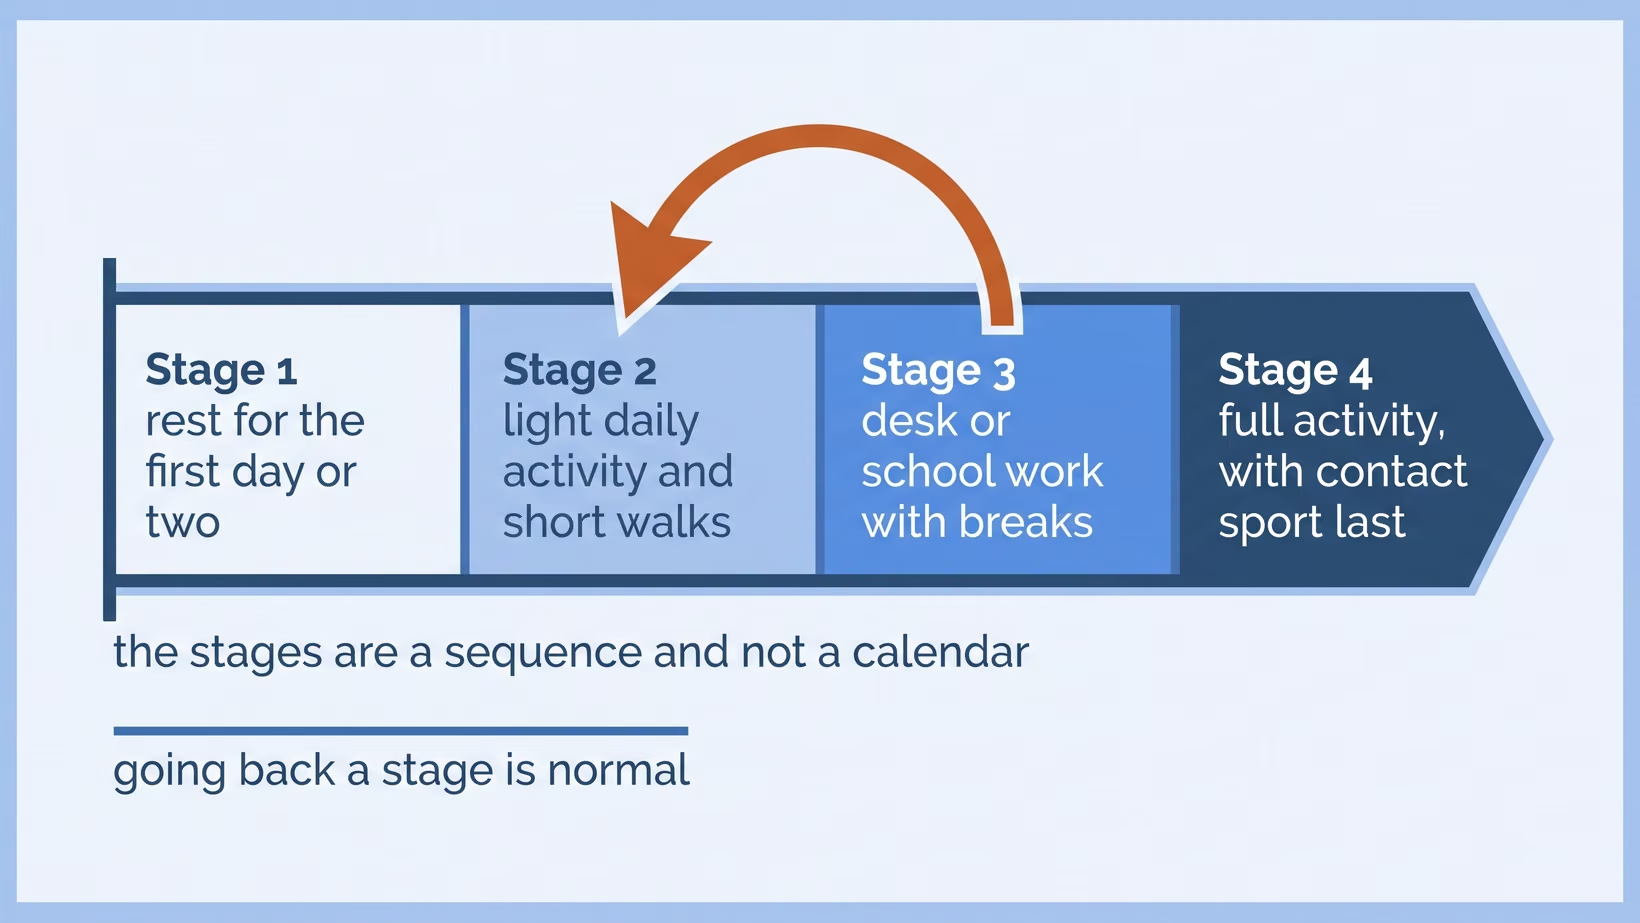
The return to work, school and sport happens in stages, not by a set date. Rest briefly, then return to light daily activity, then desk or school work with breaks, then full activity. Contact sport comes last.
Move up a stage when the current one is comfortable. If symptoms increase, go back a stage. That is part of the process.
Concussion in the elderly: why an older adult is checked more closely
An older adult is more likely to be sent for a CT scan after the same bump. In the UK guideline, an adult who lost consciousness or has a memory gap after a head injury is advised to have a CT scan if they are 65 or older, even when they look well. That person should go to the emergency room the same day.
An older patient is also watched more closely afterward. In an older adult, blood can collect slowly over days or weeks and only then start to press on the brain.
Why a blood thinner changes the plan after a head injury
Someone on a blood thinner who hits their head should go to the emergency room the same day, even if they feel well. They may be advised to have a CT scan even when there is no other reason for one.
If the first scan is normal, a bleed on a repeat scan a day later is uncommon. In studies of patients on warfarin, a blood thinner, whose first scan was clear, it happened in about 6 in 1,000. About 1 in 1,000 needed an operation or died.
Those figures are a reason not to repeat a normal scan as a routine. They are not a reason to skip the first scan. If symptoms get worse after a normal scan, go back to the emergency room now.
Never stop or change a blood thinner yourself. That decision belongs to the doctor who prescribed it.
When does a concussion need a scan?
A concussion needs a CT scan when something about the injury or the examination raises the chance of bleeding inside the skull. A suspected concussion alone is not the reason. In the UK guideline, an adult is advised to have a CT scan within one hour for any one of these:
- A Glasgow Coma Scale score of 12 or less when first seen, or below 15 two hours after the injury. The Glasgow Coma Scale is the 15-point score a doctor uses to grade how awake someone is.
- A suspected open or crushed-in skull fracture, or any sign of a fracture at the base of the skull
- A seizure after the injury
- New weakness or numbness in one part of the body
- Vomiting more than once
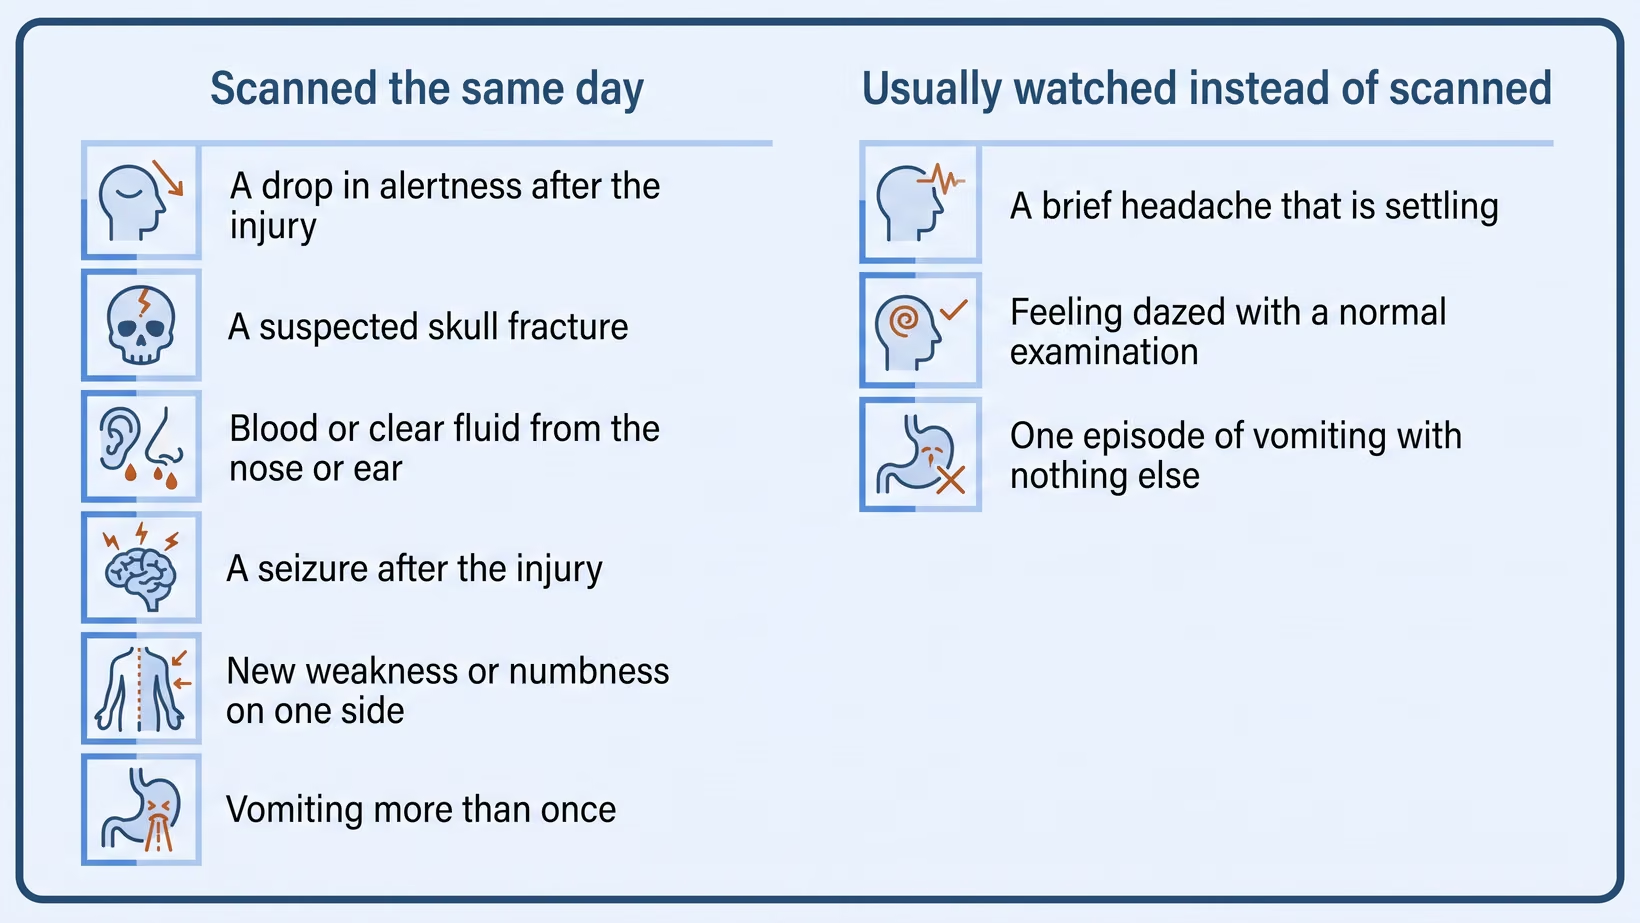
A second group is advised to have a scan within eight hours. These are adults who lost consciousness or have a memory gap and who are 65 or over, have a bleeding or clotting disorder, were hurt by a high-energy injury, or cannot remember more than 30 minutes before the impact.
What does a head CT scan show after an injury?
A head CT scan after an injury shows bleeding, a skull fracture and swelling. It is the first test used after head trauma. It is fast, widely available and good at finding those three things. A concussion does not appear on it, so a normal scan does not mean nothing happened.
A normal CT scan is good news about bleeding. A person with a normal scan can still have every symptom of a concussion, and a danger sign that appears later still means the emergency room now.
MRI or CT scan after a head injury: which one do you need?
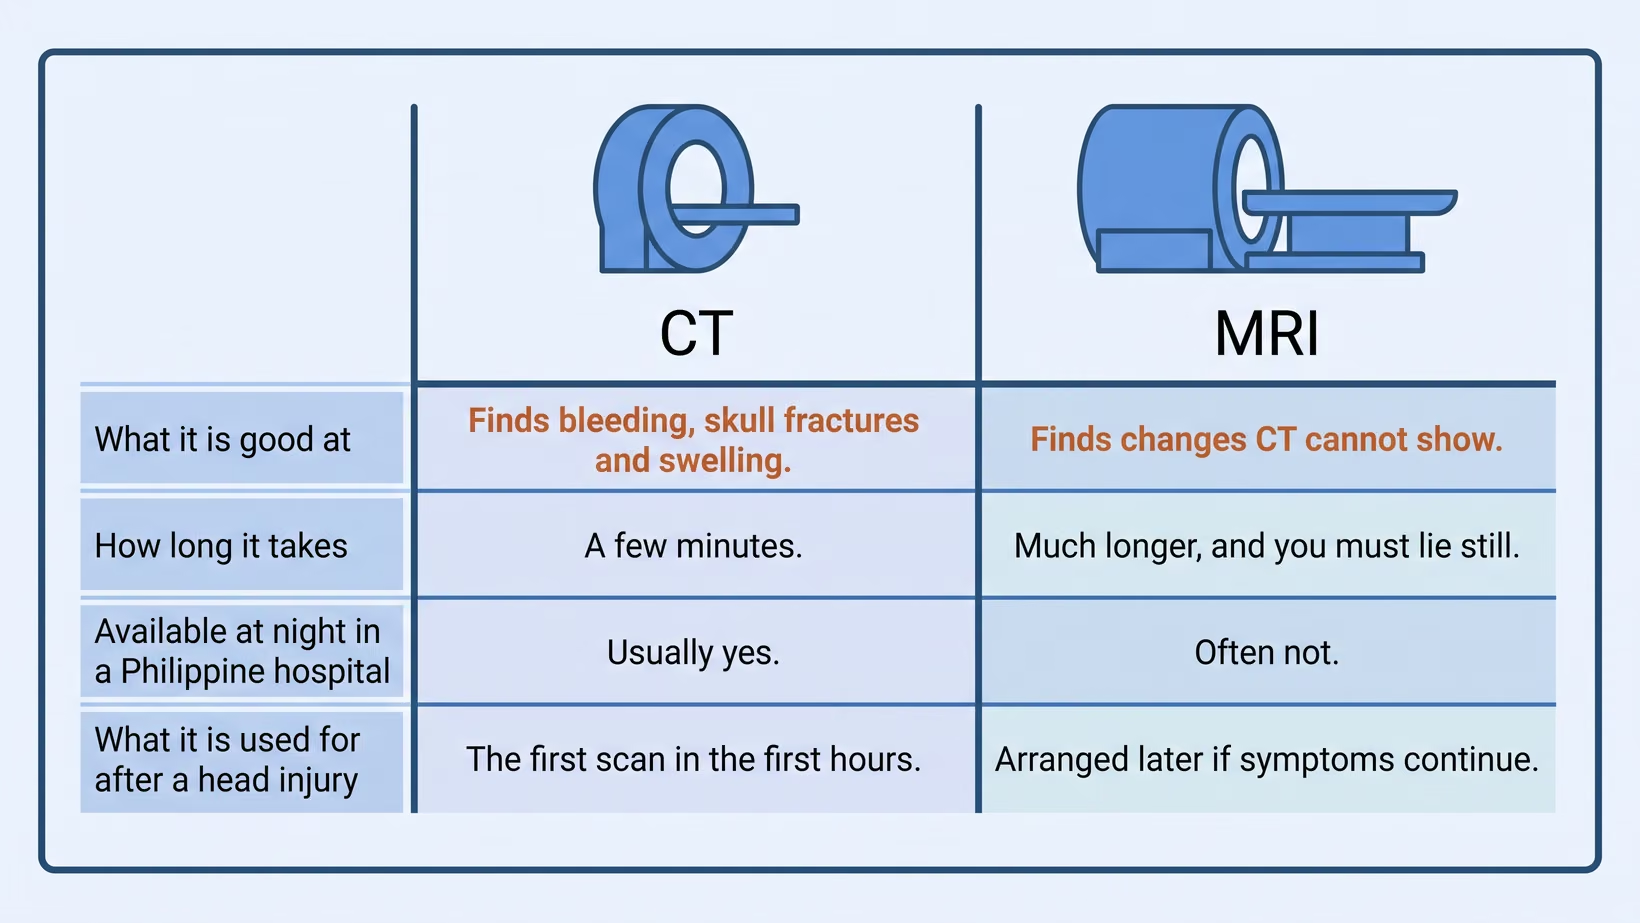
You need a CT scan first, in the hours after a head injury. A CT scan takes a few minutes and answers the urgent question: is there blood or a fracture? An MRI is usually arranged later if symptoms continue.
The UK guideline says MRI should not be the first test, for reasons of safety, practical arrangements and resources. An MRI takes much longer, and not every hospital can do one at night.
A plain skull X-ray is not the right test. A normal skull film says nothing useful about the brain underneath. The guideline says not to use skull X-rays to diagnose an important brain injury before speaking to a neuroscience unit, a hospital team for brain injury.
Head CT scan cost in the Philippines: what to ask before the scan
The cost of a head CT scan in the Philippines differs between a government hospital, a private hospital and a stand-alone imaging center, and it changes often. Before the scan, ask the radiology or billing desk for the total. Ask also what PhilHealth covers, what you pay on top, and whether you get the images and the written report.
In a government hospital, ask for the social service office and the Malasakit Center before you pay. In a private hospital, ask the billing desk whether your HMO or insurance covers an emergency head CT scan.
Concussion diagnosis criteria for primary care
The diagnosis of concussion is clinical. It rests on a plausible force to the head or body, followed by new symptoms or signs that the brain is not working as it was, with no better explanation. It does not require loss of consciousness or imaging, and a normal CT scan neither makes nor excludes it.
The international reference is the Amsterdam consensus statement on concussion in sport, with the SCAT6 and SCOAT6, the standard checks used in the clinic.
For the chart, record the date, time and mechanism of the injury, whether consciousness was lost and for how long, the span of any memory gap, the Glasgow Coma Scale score with its time, the symptoms, the neurological examination, the imaging decision with its reason, and the discharge advice.
A patient who needs a medico-legal certificate later will need that entry. It cannot be rebuilt from memory weeks afterward.
The Canadian CT Head Rule in primary care: who needs imaging
The Canadian CT Head Rule is a decision rule for adults who are alert after a minor head injury. It was built in 10 Canadian emergency departments from 3,121 patients. About 8 in 100 of those patients had a brain injury that mattered clinically, and about 1 in 100 needed urgent neurosurgical treatment, such as an operation.
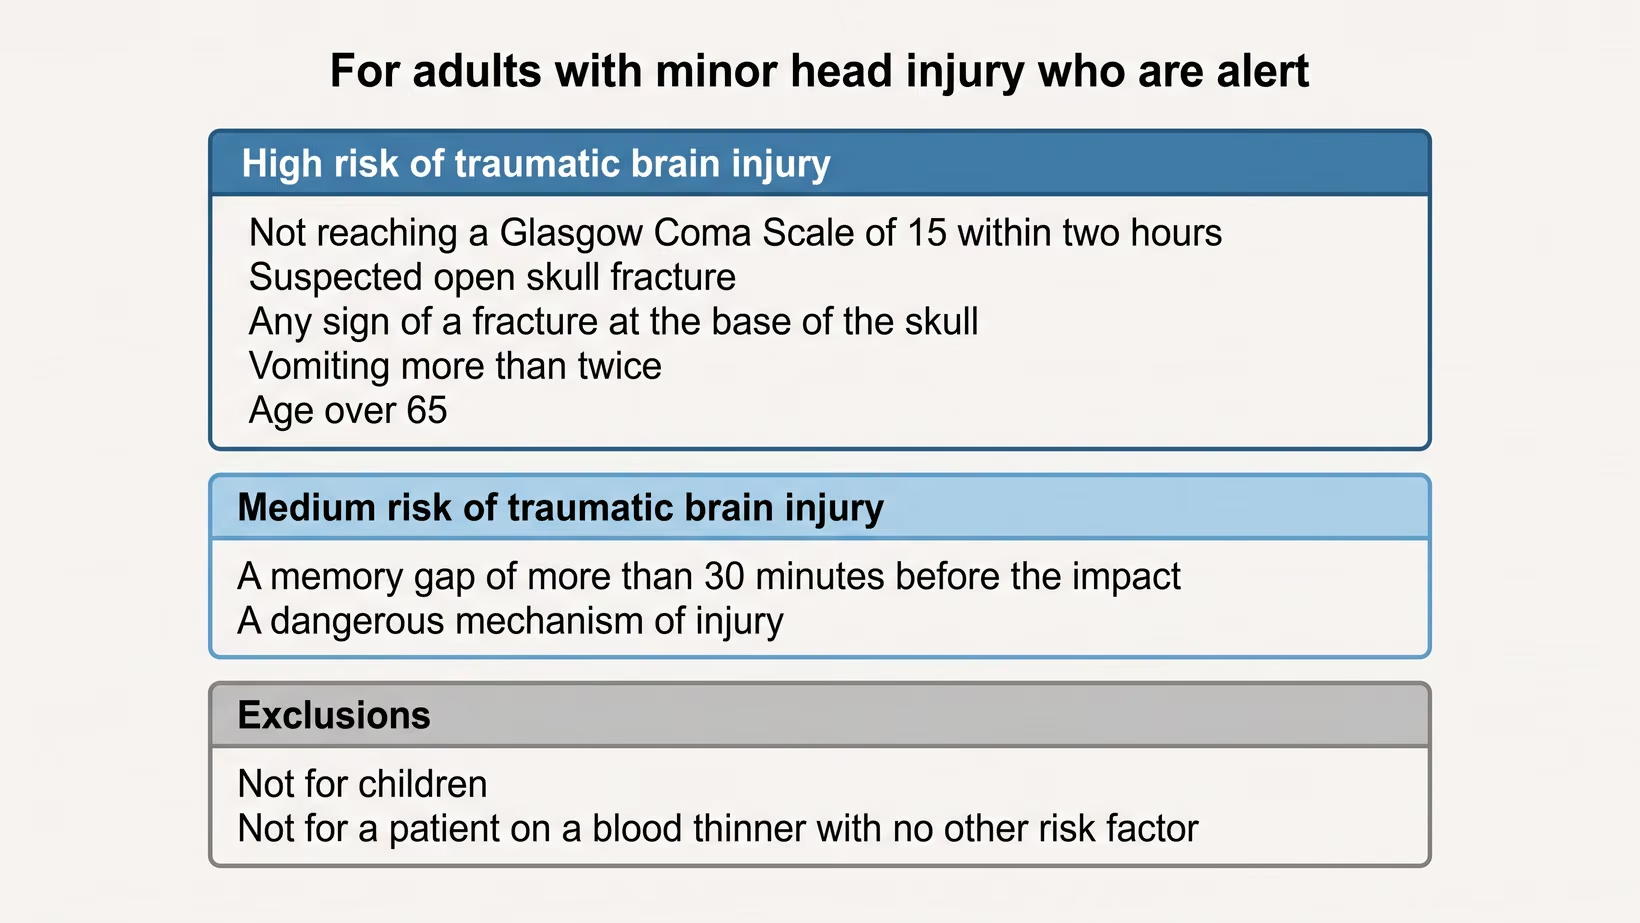
Five high-risk factors identified every patient in the study who needed urgent neurosurgical treatment: not reaching a Glasgow Coma Scale of 15 within two hours, a suspected open skull fracture, any sign of a fracture at the base of the skull, vomiting more than twice, and age over 65. Using those five would send about a third of patients for a scan.
Two medium-risk factors, a memory gap of more than 30 minutes before the impact and a dangerous mechanism of injury, found nearly all the clinically important injuries and would send about half of patients for a scan.
The rule is not for children. It is also not for a patient on a blood thinner who has no other risk factor. For that patient, the blood-thinner guidance applies instead. The rule guides the decision to scan. It does not diagnose or exclude a concussion.
When to refer a concussion, and where to send the patient
Refer a concussion to the nearest emergency department with a CT scanner, the same day, not directly to a neurosurgeon. Send by ambulance if the patient is drowsy, vomiting repeatedly, or has a new neurological finding. Call ahead to confirm the receiving hospital’s CT scanner is working overnight, so the patient is not moved twice.
The guideline list for same-day referral from a clinic is wide: a Glasgow Coma Scale below 15, any loss of consciousness, a memory gap, new weakness or numbness, a suspected skull fracture, a persistent headache, any vomiting, any seizure, previous brain surgery, a high-energy injury, a bleeding or clotting disorder, blood thinners other than aspirin alone, intoxication, a safeguarding concern, or your own doubt about the diagnosis.
Refer within the week for symptoms that are not settling after a few weeks, a mood or sleep change that is affecting work or school, or a patient who needs clearance for contact sport or a safety-critical job.
Send the mechanism and time of injury, the Glasgow Coma Scale score with its time, the examination findings, the medicine list with any blood thinner named, and the images themselves, not only the report.
There are about 174 neurosurgeons in the Philippines, roughly 1 for every 600,000 people, and 35 provinces have none at all. So a neurosurgical referral often means a transfer to another city. The local hospital with a scanner is the first stop.
For a concussion, if a neurosurgeon is available in the hospital, an emergency room consult is sought. If no neurosurgeon is available and the patient was assessed to be safe to go home, book an outpatient clinic consult with a neurosurgeon. If you are near Quezon City, you may book with my secretary. My clinic days and places are in the What to Do Now box near the top of this page.
Frequently asked questions
Can a concussion be seen on a CT scan?
No, a concussion cannot be seen on a CT scan. The scan looks for bleeding, fractures and swelling, and a concussion is an injury to how the brain works. A normal scan does not rule out a concussion.
Is it safe to sleep after a head injury?
Yes, it is safe to sleep after a head injury, as long as someone stays with you for the first 24 hours and can wake you. If they cannot wake you, or you will not stay awake, go to the emergency room now.
Can you drive after a concussion?
You should not drive after a concussion while you are dizzy, slowed, or having trouble concentrating or seeing clearly. Ask the doctor who saw you when it is safe to start again.
How soon can you go back to the gym?
You can start light movement such as walking in the first day or two after a concussion, and a clinician should set any gentle aerobic exercise. Weights, contact sport and anything with a fall risk wait until you have finished the staged return.
Can a concussion cause memory loss?
Yes, a concussion can cause a gap in memory around the time of the injury. A memory gap after a head injury is a reason to be seen in an emergency room the same day.
Does a helmet prevent a concussion?
A helmet does not make a concussion impossible. The injury comes from the brain being moved suddenly inside the skull, and a helmet cannot stop all of that movement. It is still worth wearing.
See sources
- National Institute for Health and Care Excellence. Head injury: assessment and early management. NICE guideline NG232. NICE, United Kingdom, 2023. https://www.nice.org.uk/guidance/ng232
- Stiell IG, Wells GA, Vandemheen K, et al. The Canadian CT Head Rule for patients with minor head injury. Lancet, 2001. PMID 11356436. doi 10.1016/s0140-6736(00)04561-x
- Yang LJ, Lassaren P, Londi F, et al. Risk factors for traumatic intracranial hemorrhage in mild traumatic brain injury patients at the emergency department: a systematic review and meta-analysis. Scandinavian Journal of Trauma, Resuscitation and Emergency Medicine, 2024. PMID 39289729. doi 10.1186/s13049-024-01262-6
- Leddy JJ, Burma JS, Toomey CM, et al. Rest and exercise early after sport-related concussion: a systematic review and meta-analysis. British Journal of Sports Medicine, 2023. PMID 37316185. doi 10.1136/bjsports-2022-106676
- Patricios JS, Schneider KJ, Dvorak J, et al, for the Concussion in Sport Group. Consensus statement on concussion in sport: the 6th International Conference on Concussion in Sport, Amsterdam, October 2022. British Journal of Sports Medicine, 2023. PMID 37316210. doi 10.1136/bjsports-2023-106898
- Chauny JM, Marquis M, Bernard F, et al. Risk of delayed intracranial hemorrhage in anticoagulated patients with mild traumatic brain injury: systematic review and meta-analysis. Journal of Emergency Medicine, 2016. PMID 27473443. doi 10.1016/j.jemermed.2016.05.045
- Baticulon RE, Lucena LLN, Gimenez MLA, Sabalza MN, Soriano JA. The neurosurgical workforce of the Philippines. Neurosurgery, 2023. PMID 37931081. doi 10.1227/neu.0000000000002630