Your first neurosurgery appointment is mostly talking and examination. Bring your referral letter, CT or MRI plates (the printed scan films), ideally the image files on CD or USB, a written medicine list, and someone to listen with you. It usually ends with a plan: more tests, watching and measuring again, or a later operation.
What will a neurosurgeon do on your first visit?
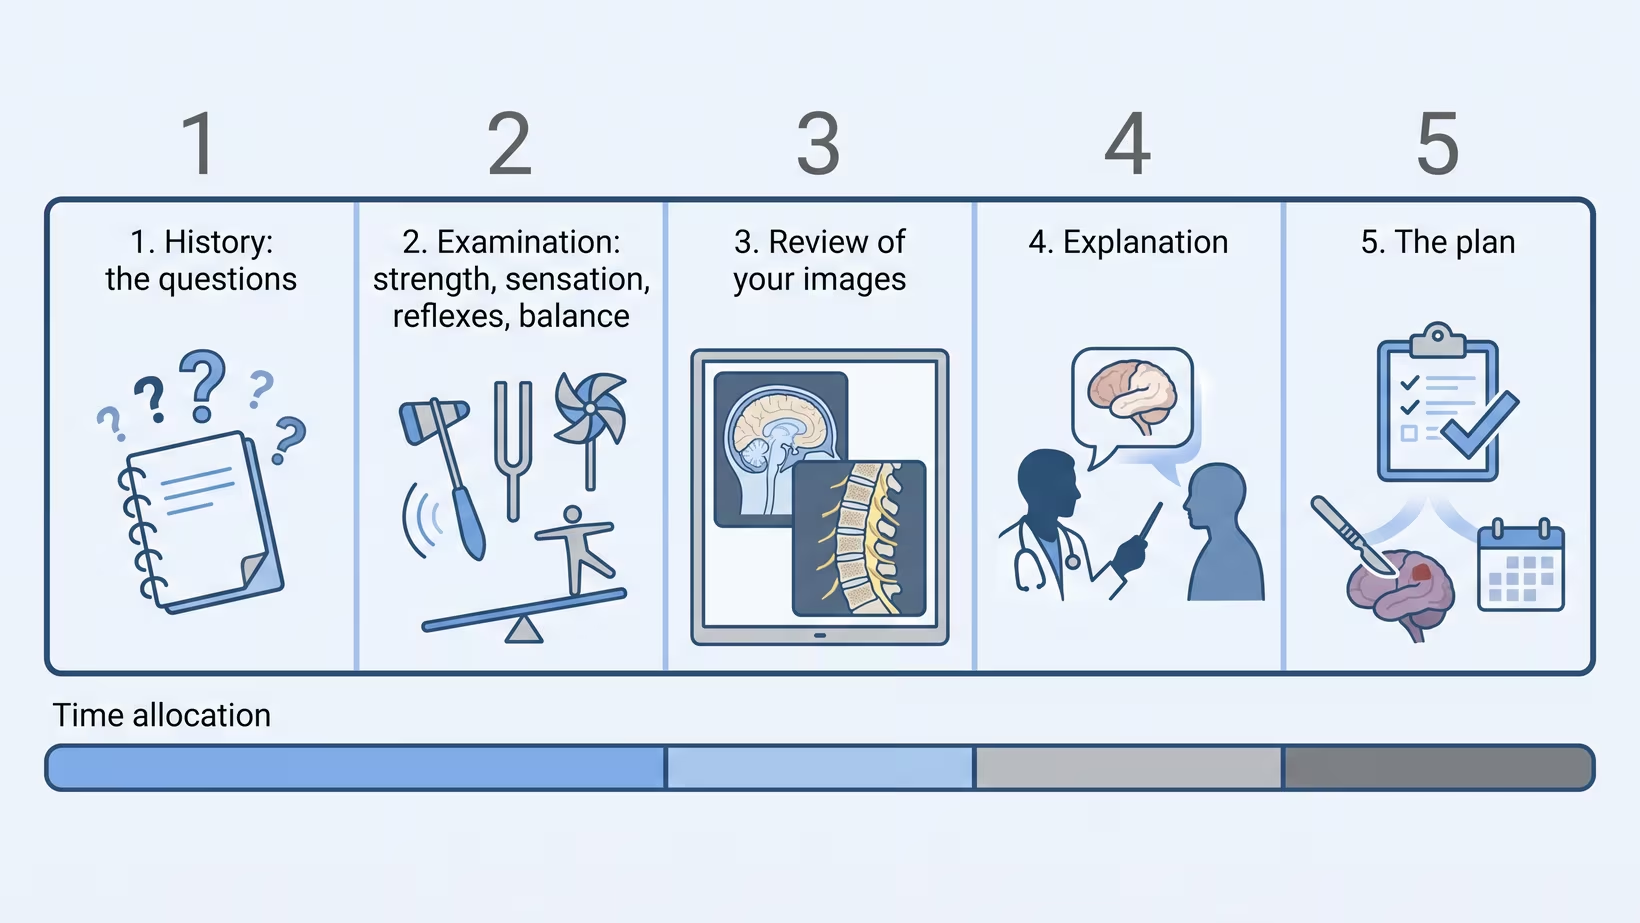
A neurosurgeon usually begins a first visit by asking questions, then examines you, then studies your images, and only then explains what is wrong and what happens next. The examination is quick and does not hurt. Very little of the hour is about the operating room.
The questions are how the diagnosis is made. In one study of new clinic patients (outpatients), the referral letter and the history together produced the diagnosis that was finally accepted in 66 of 80 patients, while the physical examination added it in only seven.
So the most useful thing you can prepare is a short opening sentence: what the trouble is, when it started, and what has changed since. In recorded consultations, patients who were allowed to finish took a median of six seconds to say what was wrong, meaning half of them needed less than that.
In the neurological examination, meaning the check of your nerves, muscles and brain function, expect the surgeon to test the strength of your arms and legs, touch your skin to check sensation, tap your tendons for reflexes, look into your eyes, check your balance, and watch you walk.
A neurosurgeon may also tell you that you do not need a neurosurgeon. That is a good outcome and not a wasted trip, and it helps to know whether your problem belongs to a neurosurgeon or a neurologist before you come.
Seek care now
When you should not wait for your appointment
Some symptoms mean the emergency room now, not the clinic in three weeks. Go to the nearest emergency department now if any of these is happening. If the documents listed below are at hand, bring them, but do not delay to look for them. Tell the triage nurse (the nurse who decides who is seen first) exactly when the symptom started:
- A headache that reaches its worst within seconds, rather than building over hours
- New or worsening weakness in an arm or a leg
- Numbness around the groin, buttocks or inner thighs
- New difficulty passing urine, or loss of control of urine or stool
- A first seizure
- Drowsiness or confusion that is getting worse, especially after a head injury
- Fever with a stiff neck
With headache, how fast it reaches its worst is one of the clearest warning signs. Among 4,536 adults who came to emergency departments with headache, a serious cause was found in about 11 in 100 of those whose headache peaked within seconds (10.9 percent), against about 7 in 100 of the rest (6.6 percent). Most such headaches have a harmless cause, but the emergency room is where that is found out, so go now.
The groin and bladder symptoms are the two that every guideline agrees on. A 2025 review of nine international guidelines found that all of them call for an urgent scan when those signs appear. Compression of the nerves at the base of the spine is understood to worsen continuously, and an expert review of the literature concludes there is no safe waiting time.

Will I be operated on right away?
You will almost never have an operation on the day of your first neurosurgery visit. A first consultation exists to decide whether an operation is needed at all. Being sent to a surgeon is not the same as being scheduled for one. When surgery is the answer, it is normally booked for a later date, after blood tests and clearance from other specialists, who confirm you are fit for the operation.
The clearest measured picture comes from spine clinics. In one series of 1,663 new spine patients in the United States, 717 of them, or about 43 in 100 (43.1 percent), were judged to be surgical candidates within six months of the first visit, which means most were not. Spine surgeons themselves describe a substantial share of referrals to them as non-operative, meaning they do not need an operation. Those figures cover spine referrals only, not brain tumor or head injury referrals.
Watchful waiting, meaning the problem is watched and checked again, is not being dismissed. It means the surgeon judges the risk of operating now to be higher than the risk of leaving the problem alone, and that the way to settle it is to measure again after a set interval. A condition where surgery is sometimes needed and sometimes not is the usual example. The exceptions to waiting are the emergencies listed above.
What to bring: your CT or MRI films and the disc
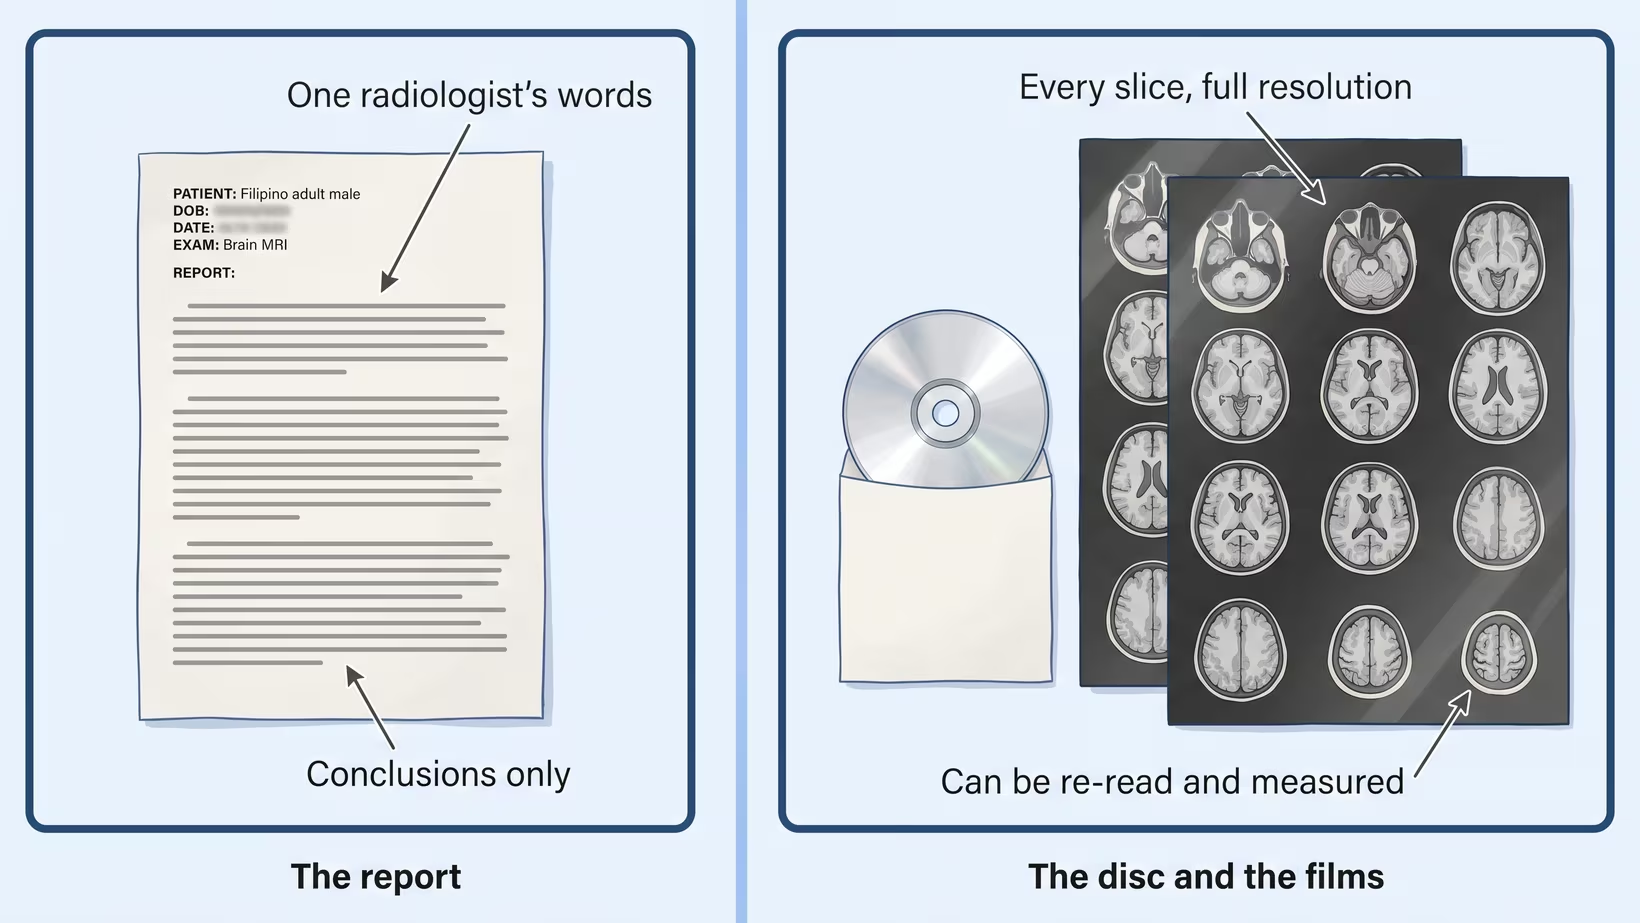
Bring the CT or MRI images themselves, not only the printed report. The report is one radiologist’s written conclusion. The disc carries every slice, which is what a neurosurgeon needs in order to look again. When you collect the study, ask the radiology department for the disc as well as the films, and say the images are for a surgeon.
- The referral letter from the doctor who sent you
- The CT or MRI disc, and the films if you have them
- The printed radiology report
- Your medicine list, or the boxes themselves
- Records of any previous operation, including the operative notes (the surgeon’s written record of what was done)
- Recent blood test results
- Your PhilHealth number and Member Data Record, your HMO card, and any approval letter you already have
- A notebook, a pen, and one companion
When brain and spine scans (neuroimaging) done elsewhere were read a second time at a referral hospital, the second reading disagreed importantly with the first in about 13 of every 100 studies (12.6 percent of 427). Those were children’s scans sent to a specialist children’s hospital, so the figure may not hold for adults.
Your medicine list, and why blood thinners matter most
Bring your medicine boxes, or a list with the exact names spelled out. One group of medicines can change what the surgeon can offer and when, and that group is the blood thinners. Never stop a blood thinner on your own.
The blood thinners include the antiplatelet medicines, which stop the small blood cells called platelets from sticking together, such as aspirin and clopidogrel, warfarin, and the newer oral anticoagulants (blood thinners you take by mouth). Herbal preparations, supplements and over-the-counter products count too. Name all of them, including the ones you take only occasionally.
Whether a blood thinner is stopped before an operation, and how long before, is a decision made between the neurosurgeon and the doctor who prescribed it. A 2024 appraisal of the guidelines covering brain surgery found the evidence thin and the balance between bleeding and clotting still unsettled, which is exactly why this is not a question to look up and settle yourself.
Bring the name of the prescribing doctor and a way to reach that clinic. It often saves a week.
Should you bring a companion?
Yes, bring one companion to your first neurosurgery appointment, because a second person helps you remember what was said. Most people forget a good part of what was said in a consultation. That is not a personal failing. Agree beforehand who writes things down and what the two of you most need answered.
Anxiety makes the forgetting worse. Among newly diagnosed patients at a fast-track cancer clinic, people recalled about 6 in 10 (60 percent) of the medical information they had been given, and the more anxious they were, the less they recalled.
Bring one person, not five. In a small pilot study of older patients, pairs who agreed these things in advance were more likely to say afterwards that the patient had understood the doctor’s explanations, and the visit did not run longer.
The listener and the decider are two separate roles. They can be the same person or two different people, but both of you should know which one you are.
Bring and ask
Questions to ask a neurosurgeon
Ask a neurosurgeon what is wrong, how sure they are, what happens if you do nothing, what your choices are, what the risks are in your case, and how long recovery takes. Write your questions down before you come, and bring the paper.
In a randomized trial of patients seeing a surgeon before an operation, those given a written question list asked more questions and recalled more of the answers, with no increase in anxiety and no lengthening of the consultation.
Your own list on your own paper is enough. A trial that compared a professionally prepared question sheet with patients simply writing their own questions found no difference in how many questions were actually asked.
About the diagnosis
- What is wrong with me, in plain words
- How sure are you, and what would change your mind
- What happens if I do nothing
About the options
- What are my choices, including the ones you are not recommending
- What does the operation involve, and how long does it take
- What are the risks in my case rather than in general
- Who will actually perform the operation, and who assists
- How many of these have you done
About afterwards
- How long in hospital, and how long before I can work
- What will I not be able to do, and for how long
- What follow-up and what repeat scans will I need
What happens after the first visit?
After the first neurosurgery visit, most patients get one of four things. A follow-up appointment, usually with a repeat scan, at a stated interval. A referral to another specialist, or to a center that does a particular operation. A date for surgery, after blood tests and clearance from other specialists. Or discharge back to the doctor who referred you, with a written explanation.
Before you leave, you should have something in writing: the plan, a prescription if one is needed, and the date or interval for coming back. The clinic normally also sends a letter to whoever referred you, and you can ask for a copy.
Ask what change in your symptoms should bring you back sooner, and write the answer down. Ask what number to call, and whether a phone call is enough or whether they need to see you. If any of the warning signs above appears while you wait, go to the nearest emergency department now; do not wait for a call back. Some problems are watched rather than operated on. For these, the follow-up matters as much as the first visit.
Neurosurgeons are few in the Philippines. In 2023 there were 174 neurosurgeons in the Philippines, roughly one for every 600,000 people, and 35 provinces had none at all. If you need to move your date, call early so that the slot can go to someone else.
Cost and PhilHealth: what to ask, and who to ask
The cost of neurosurgery depends on the hospital, on whether the admission is service (ward) or private, on the PhilHealth case rate (the set amount PhilHealth pays for your condition or operation), and on your own insurance. No exact figure can be given here, because any number written on a website goes stale.
Ask the hospital, not only the surgeon’s secretary. The billing section and the PhilHealth desk are the two places that can give you real figures.
Ask for a written estimate that separates the professional fees of the surgeon and the anesthesiologist, the hospital and operating room charges, implants or devices if any are needed, and what the PhilHealth case rate is expected to absorb.
Ask whether your surgeon and the hospital are accredited with your HMO, and ask before the date is set rather than after.
If money is the reason you are hesitating, say so out loud in the room. It changes which options are worth discussing.
What to do now
What to Do Now
If none of the warning signs above is happening, see a neurosurgeon at a clinic appointment. If any of them is happening, go to the nearest emergency department now. You can book a consultation yourself, or your doctor can refer you.
- Bring your referral letter, the CT or MRI disc and films, and the printed report
- Bring your medicine list, or the boxes, and the name of the doctor who prescribed any blood thinner
- Bring your PhilHealth and HMO details
- Bring one companion and your written questions
If you would like me to see you, I see adults at my clinic at the Lung Center of the Philippines, Room 1101, Quezon Avenue, Quezon City, on Tuesday and Thursday from 2 PM. If the trip to Quezon City is too far for you, you can book an online consult with me on the consultation page.
Frequently asked questions
How long does a first neurosurgery appointment take?
Plan for a first neurosurgery appointment to take the whole morning or the whole afternoon, not only the appointment time. The consultation itself is usually shorter than the registration, the records and the waiting around it. If you need to move your date, call early so that the slot can go to someone else.
Do I need a referral to see a neurosurgeon?
You do not always need a referral to see a neurosurgeon. Bring one if you have it, because the letter carries information no form replaces. In one study, the referral letter and the history together gave the final diagnosis in 66 of 80 patients. If you have no referral, bring whatever records and scans you already have.
What if I do not have a CT or MRI yet?
If you do not have a CT or MRI yet, come to the neurosurgery appointment anyway. The surgeon decides which scan you actually need, and coming first can save you paying for the wrong one. Bring any earlier scans you have, so the surgeon can judge whether a new one is really needed.
Can I bring my scan on a phone instead of the disc?
A phone photograph of your CT or MRI film is better than nothing, but bring the disc as well. A phone picture loses resolution and cannot be measured or re-sliced. When you collect the study, ask the radiology department for the disc and say the images are for a surgeon.
Will I need surgery because I was referred to a surgeon?
Being referred to a neurosurgeon does not mean you will need surgery. Surgeons describe a substantial share of referrals to spine surgeons as non-operative, meaning they do not need an operation. The first visit exists to decide whether you need an operation, more tests, or a repeat check later.
Can I ask for a second opinion?
Yes, you can ask another neurosurgeon for a second opinion, and you do not need permission. Bring the same disc and reports to the second doctor, and say that you have already had an opinion. Bring your written list of questions as well.
What should I wear to the appointment?
Wear loose clothing you can move in to a neurosurgery appointment, and shoes you can remove easily. The examination involves walking, bending, and testing the strength of your arms and legs. The surgeon may also check your balance and tap your tendons for reflexes.
See sources
- Hampton JR, Harrison MJ, Mitchell JR, Prichard JS, Seymour C. Relative contributions of history-taking, physical examination, and laboratory investigation to diagnosis and management of medical outpatients. British Medical Journal, 1975. PMID 1148666
- Singh Ospina N, Phillips KA, Rodriguez-Gutierrez R, et al. Eliciting the Patient’s Agenda: Secondary Analysis of Recorded Clinical Encounters. Journal of General Internal Medicine, 2019. PMID 29968051
- Roberts T, Horner DE, Chu K, et al. Thunderclap headache syndrome presenting to the emergency department: an international multicentre observational cohort study. Emergency Medicine Journal, 2022. PMID 35144978
- Hennessy O, Devitt AT, Synnott K, Timlin M. Assessment and early investigation of cauda equina syndrome: a systematic review of existing international guidelines and summary of the current evidence. European Spine Journal, 2025. PMID 40000448
- Todd NV. Cauda equina syndrome: is the current management of patients presenting to district general hospitals fit for purpose? The Bone and Joint Journal, 2015. PMID 26430015
- Broida SE, Schrum ML, Yoon E, et al. Improving Surgical Triage in Spine Clinic: Predicting Likelihood of Surgery Using Machine Learning. World Neurosurgery, 2022. PMID 35351645
- Wilson B, Gaonkar B, Yoo B, et al. Predicting Spinal Surgery Candidacy From Imaging Data Using Machine Learning. Neurosurgery, 2021. PMID 33826737
- Baticulon RE, Lucena LLN, Gimenez MLA, Sabalza MN, Soriano JA. The Neurosurgical Workforce of the Philippines. Neurosurgery, 2023. PMID 37931081
- Eakins C, Ellis WD, Pruthi S, et al. Second opinion interpretations by specialty radiologists at a pediatric hospital: rate of disagreement and clinical implications. AJR American Journal of Roentgenology, 2012. PMID 22997387
- Blazak P, Hacking C, Presneill J, Reade M. Early repeat computed tomographic imaging in transferred trauma and neurosurgical patients: incidence, indications and impact. Journal of Medical Imaging and Radiation Oncology, 2018. PMID 29399974
- Ntalouka MP, Brotis A, Karagianni MD, et al. Perioperative management of antithrombotics in elective intracranial procedures: systematic review, critical appraisal. Acta Neurochirurgica, 2024. PMID 38383680
- Wolff JL, Roter DL, Barron J, et al. A tool to strengthen the older patient-companion partnership in primary care: results from a pilot study. Journal of the American Geriatrics Society, 2014. PMID 24417565
- Wolff JL, Boyd CM, Gitlin LN, Bruce ML, Roter DL. Going it together: persistence of older adults’ accompaniment to physician visits by a family companion. Journal of the American Geriatrics Society, 2012. PMID 22211465
- Ey JD, Herath MB, Reid JL, et al. Improving communication and patient information recall via a question prompt list: randomized clinical trial. British Journal of Surgery, 2023. PMID 37768034
- Bottacini A, Goss C, Mazzi MA, et al. The involvement of early stage breast cancer patients during oncology consultations in Italy: a multi-centred, randomized controlled trial of a question prompt sheet versus question listing. BMJ Open, 2017. PMID 28801395
- Nguyen MH, Smets EMA, Bol N, et al. Fear and forget: how anxiety impacts information recall in newly diagnosed cancer patients visiting a fast-track clinic. Acta Oncologica, 2018. PMID 30264632