An acute subdural hematoma is fresh blood collecting between the surface of the brain and the tough membrane just inside the skull, usually within hours of a head injury. It is an emergency because the clot keeps pressing on the brain. Guidelines say that once there is a reason to operate, the clot should be removed as soon as possible.
What is an acute subdural hematoma?
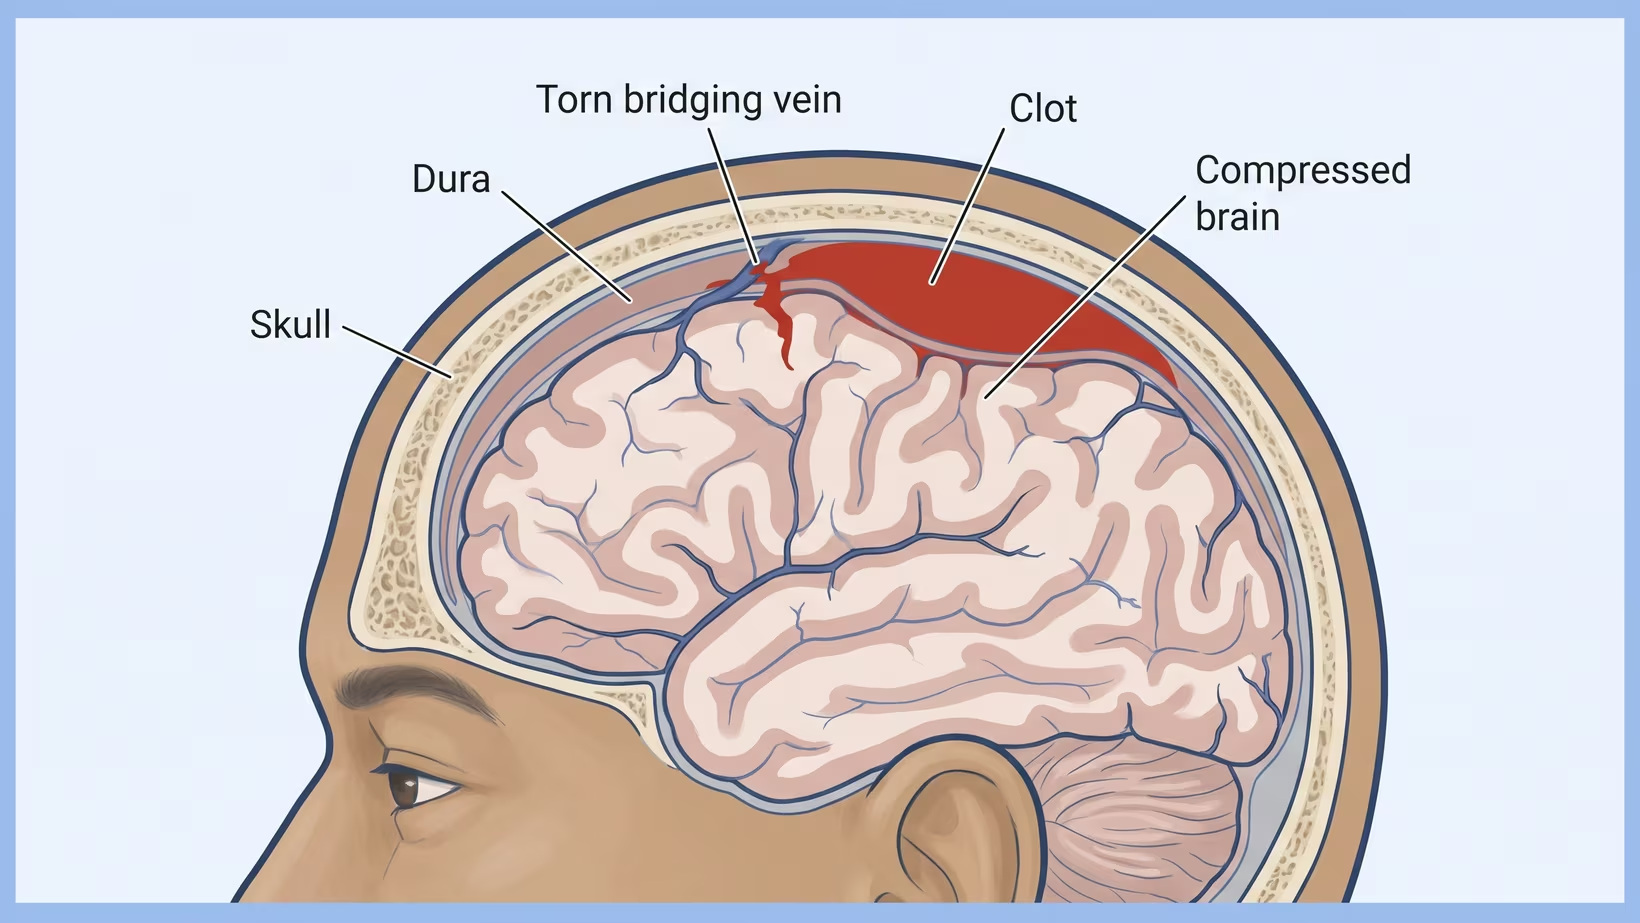
An acute subdural hematoma is a collection of fresh blood in the subdural space, the thin gap between the brain’s surface and the dura, which is the tough leathery covering just inside the skull. Acute means the blood is new, appearing within hours to a day or two of the injury.
Small veins cross that gap to drain blood away from the brain’s surface. A blow or a sudden deceleration can tear one of these bridging veins. Blood then spreads over the surface of the brain in a thin crescent shape. Because the skull cannot expand, every milliliter added has to push the brain aside.
How is this different from a chronic subdural hematoma?
Timing, and the state of the blood. An acute collection is fresh clot that appears within hours to days and looks bright on a CT scan, a picture of the brain made with X-rays. A chronic subdural hematoma is an older collection that has broken down into fluid, and it usually appears weeks after a bump that may have seemed minor, in an older person. The two are drained differently, and the symptoms that appear weeks after hitting your head belong to the chronic form.
Who is most at risk, from newborn to elderly
This injury happens at every age, and the setting changes with the age. Blood thinners matter too: a recognized guideline counts anticoagulant (blood thinner) treatment or a clotting disorder among the reasons an adult with a head injury needs a scan. In infants and young children, subdural bleeding is one of the findings linked to inflicted head injury, and that possibility is checked whenever the story does not fit the injury. Do not delay bringing a child in because of this.
Seek care now
When to go to the emergency room after a head injury
Go now if any of the following follows a head injury. Do not wait for morning, and do not phone for advice instead of bringing the person in.
- The person will not wake, or is drowsy and hard to rouse
- Confusion, strange behavior, or asking the same question again and again
- Vomiting twice or more
- A seizure
- One pupil larger than the other
- New weakness on one side, slurred speech, or a change in walking
- A headache that keeps getting worse
- Clear fluid or blood coming from the nose or the ear
- Any loss of consciousness, however brief
- The person takes a blood thinner or has a bleeding disorder
In a baby, raised pressure in the head can make the soft spot tense or bulging, and a baby may cry in a way you cannot settle or go limp. A baby with any of these after a head injury needs to go now.
Go to the nearest emergency room now. If one with a CT scanner and a neurosurgeon on call is just as close, choose it, but do not drive past an emergency room to look for one when the person will not wake, is having a seizure or is struggling to breathe.
If they are at hand, bring the list of medicines, any previous scans, and the time the injury happened, written down. Do not delay leaving to look for them.
A head injury in an elderly person after a fall deserves the same trip even when the fall looked trivial.
For clinicians, the Scandinavian Neurotrauma Committee guideline recommends a CT in adults after mild or moderate head injury with a GCS of 14 or below, loss of consciousness, two or more episodes of vomiting, anticoagulant treatment or a coagulation disorder, clinical signs of a depressed or basal skull fracture, a post-traumatic seizure, or a focal neurological deficit. That guideline covers adults only, and it is not Philippine policy.
Why does the surgery have to be within hours?
Because the clot can keep growing and the brain can keep swelling, and the skull gives no room for either. Bleeding inside the head after a head injury can push the brain out of position and kill, and that is what the whole emergency is about. The guidelines put it plainly: in a patient with an acute subdural hematoma and an indication for surgery, the clot should be evacuated as soon as possible.
Notice what the guideline does not say. It does not name a number of hours. So “hours” describes how fast the team has to move. It is not a deadline that has already passed. If the person is still at home with any of the warning signs above, go now.
The only trial evidence on timing here is about a medicine, not surgery. In CRASH-3, a trial of a medicine given in hospital rather than of an operation, treating sooner worked better than treating later in mild and moderate head injury, while the timing made no obvious difference in severe injury.
What does the pressure on the brain actually do?
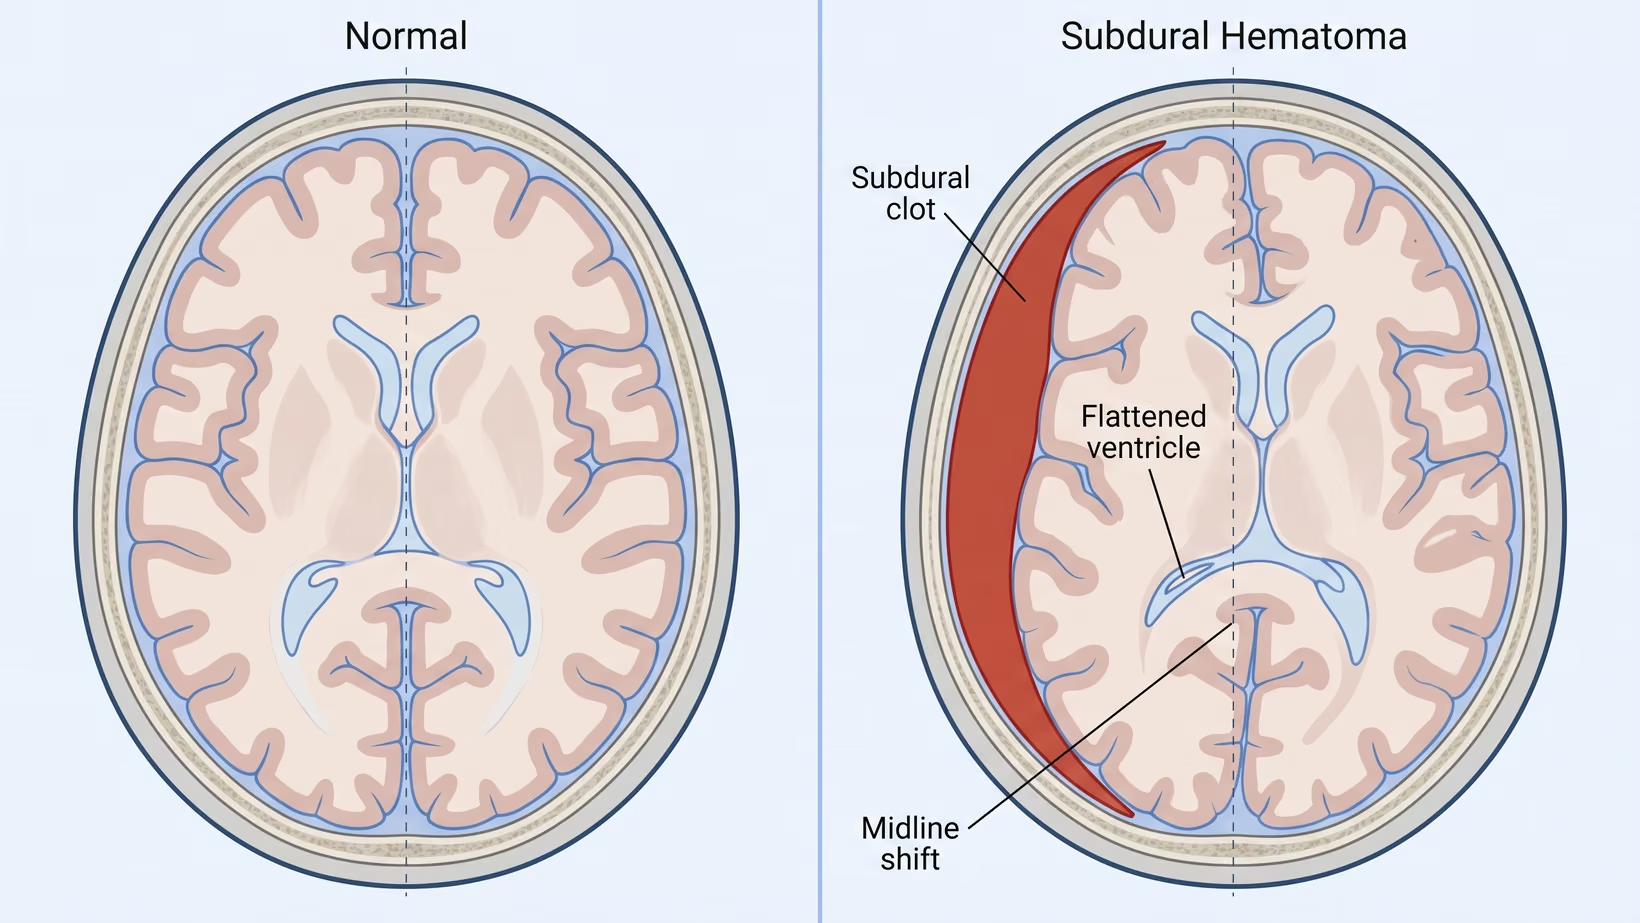
The skull is a closed box, so a clot inside it can only make room by squeezing something else. First the fluid spaces give way: the ventricles, the fluid-filled chambers inside the brain, flatten and the cisterns, the fluid spaces at the base of the brain, narrow. Then the brain itself is pushed across the midline, away from the clot.
If the pressure keeps climbing, brain tissue is forced through the openings it normally sits above. That is herniation, meaning the brain is pushed out of its normal place, and it is how bleeding inside the head after an injury can kill.
This is why a measured number matters more than an impression. Pressure inside the skull cannot be judged from the bedside once a patient is unconscious, so the guidelines recommend that every patient in coma with an acute subdural hematoma has intracranial pressure monitored, usually through a fine probe passed through the skull. That is also why a monitor is often placed even after the clot has been removed.
The coma score the doctors keep saying: what GCS means
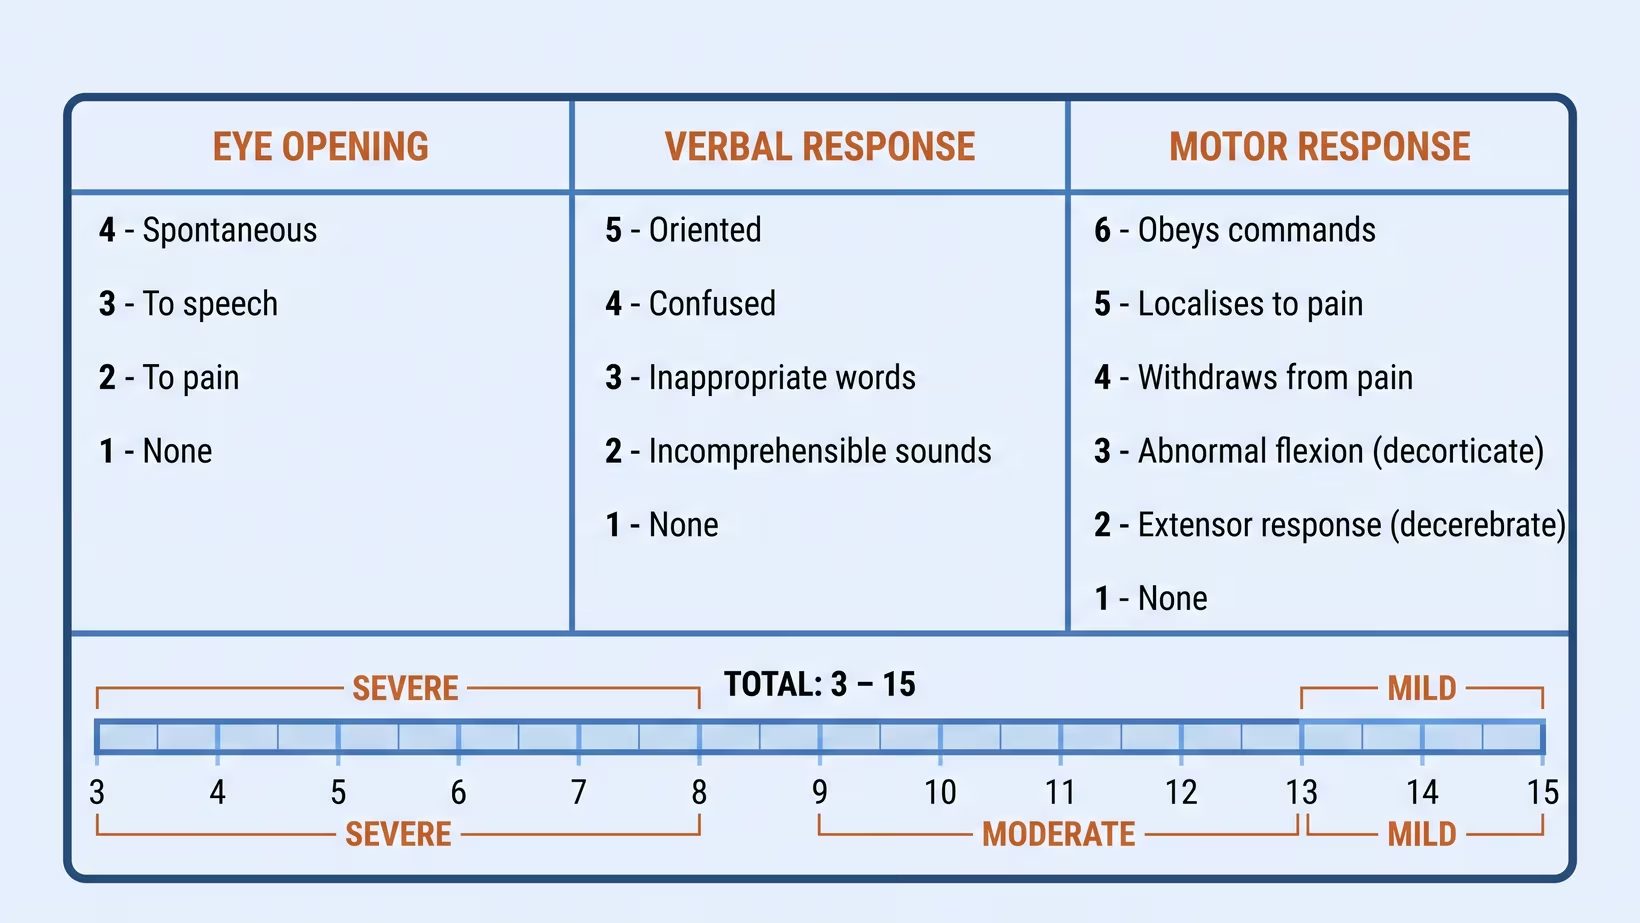
The Glasgow Coma Scale, or GCS, is a score out of fifteen that describes how awake someone is, and the team repeats it because it is the number that tracks change. It adds three observations together: whether the eyes open, what the patient can say, and how the limbs move. The lowest possible total is three, and fifteen is fully awake and oriented.
A total of less than nine is what the guidelines call coma, and that threshold is written into the surgical criteria for this injury.
The score is not hospital jargon. In a prognostic study of more than ten thousand patients with head injury, the Glasgow Coma Scale was one of four bedside findings that independently carried information about outcome, alongside age, how the pupils react to light, and major injuries elsewhere in the body. That is information about groups of patients rather than a prediction for one person, so a single number cannot tell a family what will happen.
What the scan showed, line by line
The CT report is a list of the features that change the plan, and it is worth reading in order. The clot itself is described by where it sits and how thick it is, in millimeters. Midline shift is how far the middle of the brain has been pushed across, also in millimeters.
Then come the spaces. A third ventricle or basal cisterns described as obliterated means those fluid spaces have been squeezed shut. Subarachnoid blood means bleeding has also spread into the fluid layer over the brain’s surface. Small scattered bleeds within the brain are reported as petechial hemorrhages.
Those same features, along with a hematoma that has not been evacuated, are the ones that carried information about a patient’s outcome in the large CT model built from head injury patients. That model predicted less well in low and middle income countries, so it is not a calculator to apply to one Philippine patient.
A first scan is one moment. Guidelines for adults with milder head injuries recommend repeating the CT if the patient deteriorates neurologically or the coma score falls by two points or more, which is why the scan is often done again.
How the surgeon decides to operate
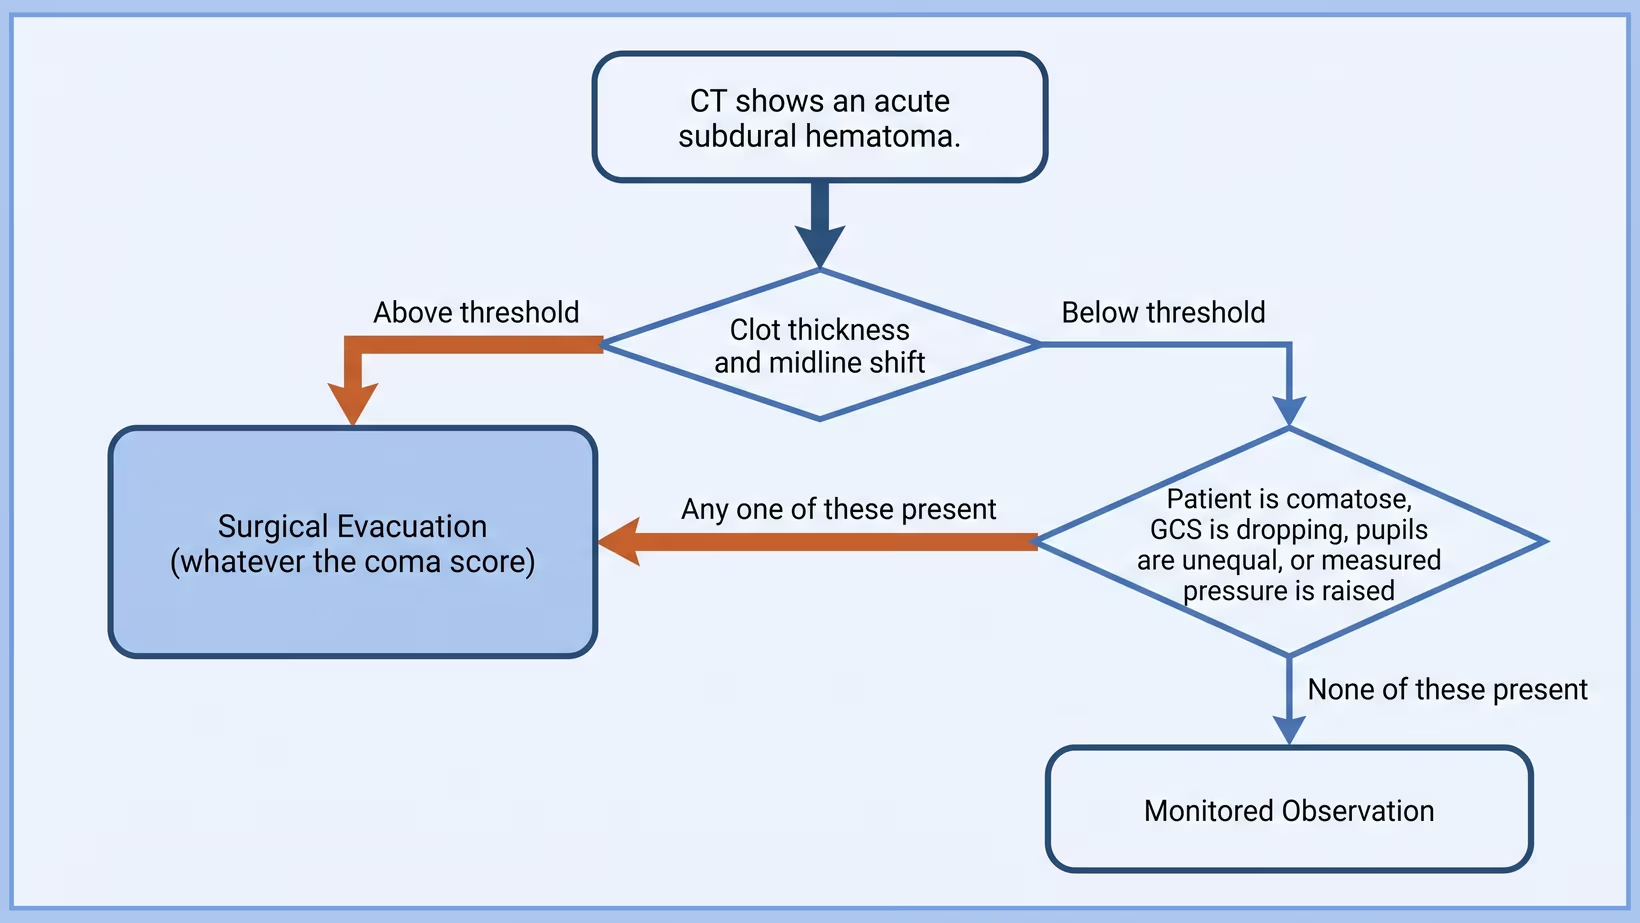
Two things decide it: what the scan shows, and what the patient is doing clinically. When the clot is large enough on its own, the scan decides, and surgery follows whatever the coma score. When the clot is smaller, the patient’s condition decides.
For a comatose adult with a GCS under nine, a clot thinner than 10 mm and a shift of less than 5 mm, the guidelines still say evacuate if any of three things is true. The coma score has fallen by two or more points between the injury and arrival at hospital. The pupils are unequal, or fixed and dilated. Or the measured pressure inside the head is above 20 mm Hg.
Each of those says the brain is losing the argument with the clot. The pressure figure comes from a monitor placed in hospital, and nobody can judge it from outside. Where none of them is present, close observation may be chosen instead, which is when a subdural hematoma is watched instead of operated on.
The thickness and shift numbers that decide surgery
The two numbers are 10 mm and 5 mm. The Brain Trauma Foundation guideline states that an acute subdural hematoma thicker than 10 mm, or one causing a midline shift greater than 5 mm on CT, should be surgically evacuated regardless of the patient’s Glasgow Coma Scale score.
Look at what “regardless” is doing in that sentence. A patient can be talking, oriented and apparently well, and still meet the threshold for an operation, because the clot is already displacing the brain.
Read the measurements for what they are. They are a threshold for offering surgery, not a prognosis (an expected outcome) and not a score that predicts the result. They were set for adults, and they were not established in children, whose skulls and brains behave differently. Surgeons and hospitals still weigh the whole patient: the age, the other injuries, and what the family is being asked to consent to.
What happens in the operating room?
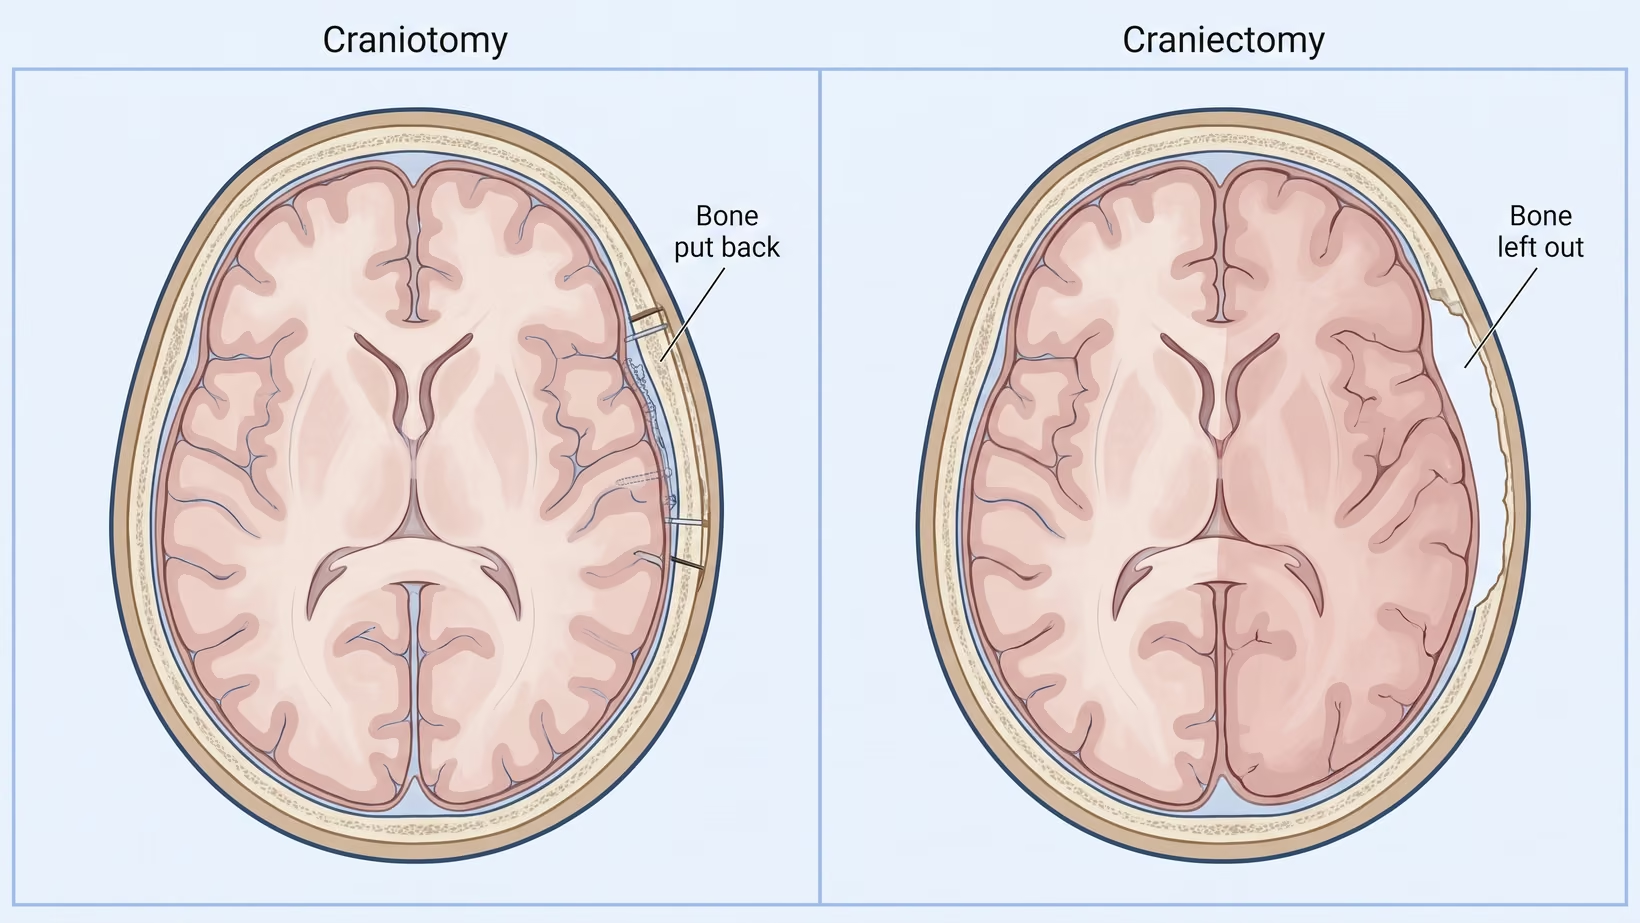
The clot is removed through a craniotomy, which means a piece of the skull is lifted out so the surgeon can reach the brain’s surface and clear the blood away. For a comatose patient, the guideline describes exactly that: evacuation through a craniotomy, with or without removal of the bone flap, and with or without opening and patching the dura.
The decision families hear about is whether the bone goes back. In a craniotomy the bone flap is replaced and fixed at the end of the operation. In a decompressive craniectomy the piece of bone is left out and the scalp is closed over it, which gives a swollen brain somewhere to expand.
A randomized trial of 450 patients compared the two approaches in this exact injury. Disability and quality of life at follow-up were similar either way. More patients in the craniotomy group needed further surgery, and more patients in the craniectomy group had problems with the wound. So the choice is a surgical judgment made in the room, not one operation being plainly better.
What the team watches for in the first days after surgery
The pressure inside the skull, the pupils, and the coma score, over and over. Guidelines recommend that a patient in coma has the pressure inside the skull monitored, and the team repeats the scan if the neurological state or the coma score falls. Numbers are followed rather than impressions, because sedation and a breathing tube make the bedside picture hard to read. What recovery looks like from there is a separate question, and it is covered in survival after acute subdural hematoma surgery.
What to do now
Transferring a patient who needs a neurosurgeon
Start the referral while the patient is still being stabilized, not after. Images that travel with the patient are images the receiving team does not have to wait for, and the neurosurgeon at the other end can only decide from what actually arrives.
Send with the patient:
- The CT images themselves, not only the report
- The coma score, with the time it was taken, and the trend since arrival
- Pupil size and reaction on both sides
- Any blood thinner or antiplatelet, with the time of the last dose
- Airway status, blood pressure and oxygen saturation
- The mechanism and the time of injury
- The name and number of the receiving neurosurgeon, agreed before the ambulance leaves
Delay here has been measured. A published comparison of pediatric head injury care at one hospital in the Philippines with one center in the United States found longer times at the Philippine hospital: 12.3 hours versus 6.5 to a consult, 12.0 versus 2.8 to imaging, and 45.4 versus 5.6 to surgery. Those figures describe children at one referral hospital. They are not a national average and not a prediction for any individual patient, and they are a reason to make the call early.
After the emergency, a patient who has gone home can be seen in a neurosurgeon’s outpatient clinic. You may refer the patient to me, or the family may book directly:
- Adults: my clinic at the Lung Center of the Philippines, Quezon City, Tuesday and Thursday from 2 PM
- Children: my clinic at the Philippine Children’s Medical Center (PCMC), Quezon City, Wednesday from 2 PM
- Families too far away to travel: an online consult, booked on the consultation page
Frequently asked questions
Is an acute subdural hematoma the same as a concussion?
No. A concussion is a disturbance of brain function after a bump to the head, while an acute subdural hematoma is a collection of blood that a CT scan can show and that may need an operation. Both can follow the same accident, which is why the scan is what settles the question.
Can an acute subdural hematoma get better without surgery?
Sometimes, when the clot sits below the guideline thresholds for thickness and shift and the patient stays awake and stable. That decision is made in hospital and watched closely, because a clot that grows or a coma score that falls changes the answer.
Why did the scan look almost normal at first?
A scan is a photograph of one moment, and a bleed can be small when the first picture is taken. Guidelines for adults with milder head injuries recommend repeating the CT if the patient deteriorates neurologically or the coma score falls by two points or more, which is exactly why the team keeps rechecking.
What does it mean when the pupils are unequal?
It is a sign the team acts on immediately. Unequal, or fixed and dilated, pupils are one of the findings the guidelines list as a reason to operate on a comatose patient even when the clot is thin, and pupil reaction is one of the four factors that carried prognostic weight in a large head injury study. Tell the nurse the moment you notice it.
The patient is on a blood thinner. Does that change anything?
It changes what happens next. A guideline lists anticoagulant treatment or a clotting disorder among the reasons an adult with a head injury needs a CT scan, even when the injury looked minor. Bring the name of the medicine and the time of the last dose, because the team will ask for both.
Bring and ask
What do we ask the doctor before signing the consent?
Ask about the operation itself, and about what happens after it. These are the questions that get useful answers:
- Which operation is planned, and will the bone be put back at the end?
- Will a pressure monitor be placed?
- What is the plan if the next scan is worse?
- What will you be able to tell us in the first 24 hours, and who will tell us?
- Who do we talk to about the bill and about PhilHealth coverage for this admission? (Ask this, but do not hold the consent for an emergency operation while you wait for the answer.)
For that last one, ask the billing section of the receiving hospital and the PhilHealth desk in the same building. What an admission like this costs depends on the hospital, the length of stay and what the operation turns into, so ask the people holding the actual account rather than working from a figure found online.
See sources
- Bullock MR, Chesnut R, Ghajar J, Gordon D, Hartl R, Newell DW, Servadei F, Walters BC, Wilberger JE; Surgical Management of Traumatic Brain Injury Author Group. Surgical management of acute subdural hematomas. Neurosurgery, 2006;58(3 Suppl):S16-24. PMID 16710968.
- Hutchinson PJ, Adams H, Mohan M, et al; RESCUE-ASDH Collaborative Group. Decompressive craniectomy versus craniotomy for acute subdural hematoma. New England Journal of Medicine, 2023. PMID 37092792. doi:10.1056/NEJMoa2214172.
- CRASH-3 trial collaborators. Effects of tranexamic acid on death, disability, vascular occlusive events and other morbidities in patients with acute traumatic brain injury (CRASH-3): a randomised, placebo-controlled trial. The Lancet, 2019. PMID 31623894. doi:10.1016/S0140-6736(19)32233-0.
- Perel P, Arango M, Clayton T, et al; MRC CRASH Trial Collaborators. Predicting outcome after traumatic brain injury: practical prognostic models based on large cohort of international patients. BMJ, 2008. PMID 18270239. doi:10.1136/bmj.39461.643438.25.
- Unden J, Ingebrigtsen T, Romner B; Scandinavian Neurotrauma Committee. Scandinavian guidelines for initial management of minimal, mild and moderate head injuries in adults: an evidence and consensus-based update. BMC Medicine, 2013. PMID 23432764. doi:10.1186/1741-7015-11-50.
- Rolle ML, Pascual JSG, Williams AL, West T, McLellan R, Khu KJO, Baticulon RE, Duhaime AC. Time to care: analysis of time differences and outcomes in the management of pediatric traumatic brain injury for a high-income and lower-middle-income country. World Neurosurgery, 2023. PMID 37121503. doi:10.1016/j.wneu.2023.04.094.
- Karibe H, Hayashi T, Hirano T, Kameyama M, Nakagawa A, Tominaga T. Surgical management of traumatic acute subdural hematoma in adults: a review. Neurologia Medico-Chirurgica (Tokyo), 2014;54(11):887-94. PMID 25367584. doi:10.2176/nmc.cr.2014-0204.
- Piteau SJ, Ward MGK, Barrowman NJ, Plint AC. Clinical and radiographic characteristics associated with abusive and nonabusive head trauma: a systematic review. Pediatrics, 2012;130(2):315-23. PMID 22778309. doi:10.1542/peds.2011-1545.