A meningioma is a tumor that grows from the meninges, the layers that cover the brain, rather than from brain tissue itself. It is the most common primary brain tumor, and most are not cancer. Many are found by accident on a scan and if small, are monitored rather than removed.
What does meningioma mean?
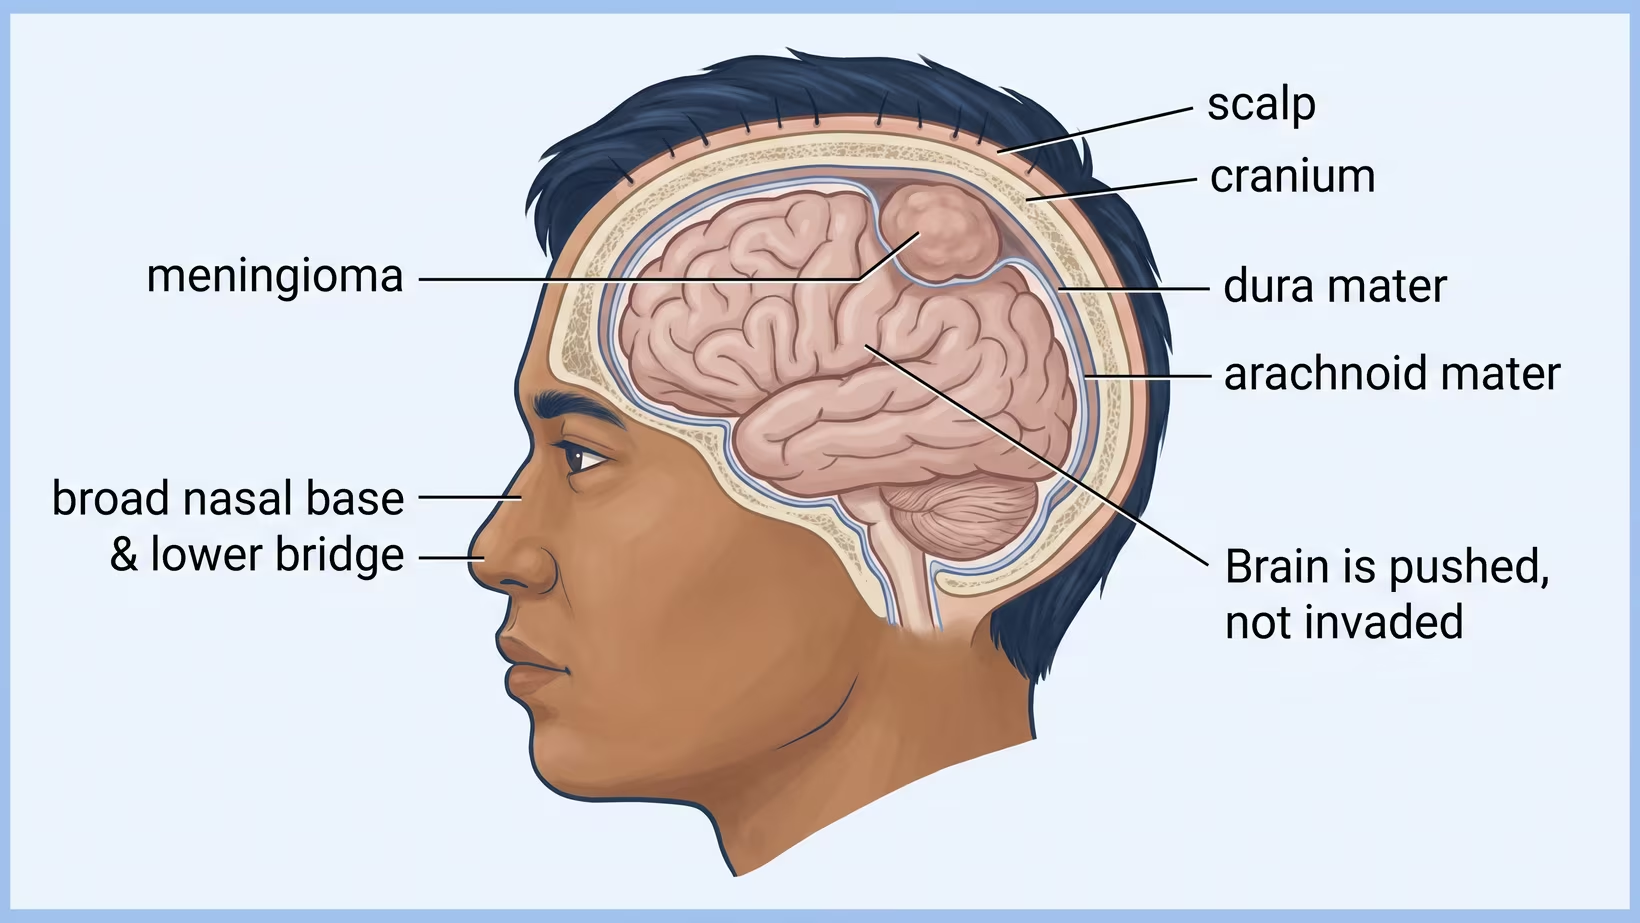
A meningioma is a growth that starts in the meninges, the covering layers wrapped around the brain, and not in brain tissue. The word joins two parts: meninges, the coverings, and the ending oma, which means a growth. The tumor sits on the brain and presses on it from outside.
Those coverings have names you will see in a report. The dura is the tough outer layer that lines the inside of the skull. The arachnoid is the thin, delicate layer beneath it. Under that is a space filled with fluid, and then the pia, a very fine layer lying on the brain itself.
A tumor that starts outside the brain can often be separated from it. The trouble it causes usually comes from pressure on what sits next to it. A small number grow into the brain surface, and these are graded higher.
In most people, no cause is ever identified. A few things are known to raise the risk: radiation to the head in the past, long-term use of certain high-dose hormone medicines, and some inherited conditions that run in families. Tell your doctor about any of these. Do not stop a hormone medicine on your own; ask the doctor who prescribed it.
Is a meningioma a benign brain tumor, or is it cancer?
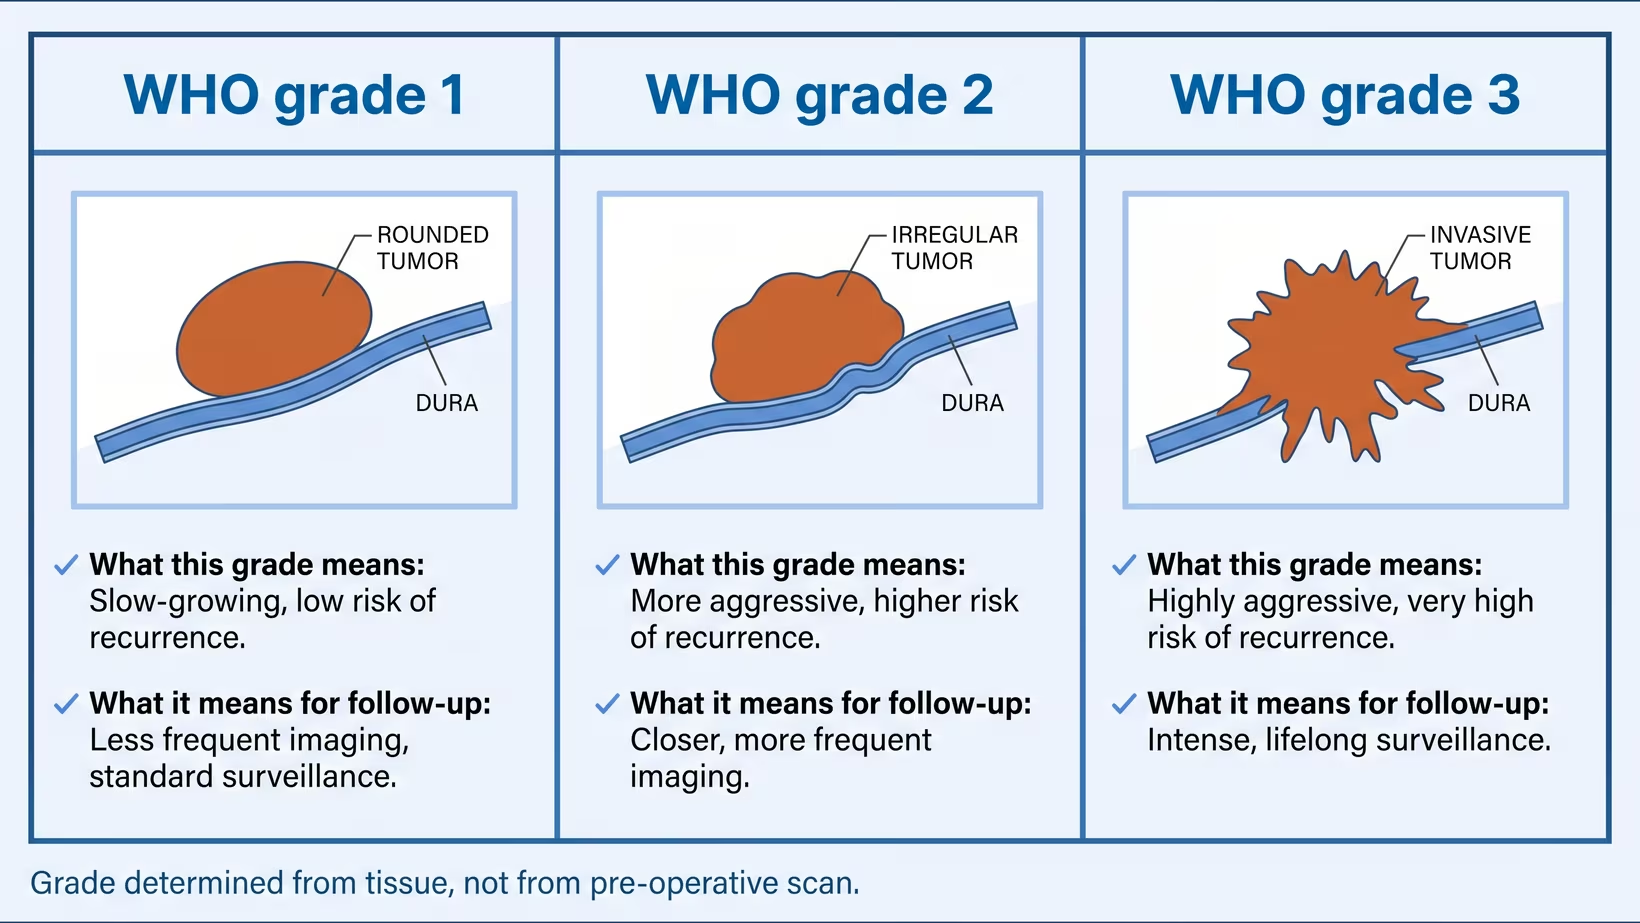
Most meningiomas are not cancer. Benign, meaning not cancer, describes how the cells look and behave under a microscope. It does not mean harmless, because a slow growth in a closed space can still cause problems. The grade comes from the tumor tissue, not the scan. A pathologist checks it under a microscope using a World Health Organization standard.
Since 2021 that standard adds molecular testing, a test of the tumor’s genes, to what is seen under the microscope. Your report may or may not include molecular testing. Among meningiomas found by accident and then operated on, the great majority are the slowest growing grade. A small number are more active and need closer follow-up. As a group, benign tumors have a far better outlook than malignant (cancerous) brain tumors.
How fast does a meningioma tumor grow?
Most meningiomas grow slowly, and some do not grow measurably at all. Growth is not judged from one scan. It is judged by comparing a new scan with an earlier one. That is why a repeat scan is often the next step, rather than an operation.
About 1 in 3 meningiomas is found by accident, on a scan done for another reason. Among those watched rather than treated, only a small number develop symptoms. About 1 in 4 eventually has some treatment, on average around two years after the tumor was found.
A larger tumor and swelling in the brain around it are linked with a higher chance of developing symptoms. When a watched meningioma does change, it usually does so within the first five years after diagnosis. Keep the scans your neurosurgeon schedules, even if the tumor has been stable for five years.
So look for any older head scan you may have. A scan from four years ago lets the doctor measure how fast the meningioma grows instead of guessing.
What symptoms does a meningioma cause?
Many meningiomas cause no symptoms and are found when a scan is done for something else. When symptoms do appear, they usually build up slowly over weeks or months, not in an instant. What people notice most often is a new headache, a seizure, weakness on one side, or a change in vision or memory.
The full list:
- Headache that is new, or different from the headaches they are used to
- A seizure, which is one of the recognized signs of a meningioma above the base of the brain
- Weakness, numbness or clumsiness affecting one side
- Change in vision, or in hearing
- Loss of the sense of smell
- Gradual change in memory, mood or personality, which in an older adult is often what the family notices first
Speed is the clue. Weakness or numbness that appears within minutes is not the pattern of a meningioma. It is more like the sudden start that points to a stroke. If weakness, numbness or trouble speaking comes on within minutes, go to the nearest emergency room now, even if it seems to be passing. A change that develops over weeks is the pattern that needs a scan.
Seek care now
When to see a doctor about a meningioma
See your doctor or a neurosurgeon within a day or two if neurological function, meaning strength, feeling, speech, vision or thinking, is getting worse over days to weeks. Do not wait for the next scheduled appointment. Go to the nearest emergency room now, or call for emergency help, for a first seizure, for sudden severe symptoms, or for any drop in alertness.
Go to the nearest emergency room now for any of these:
- A first ever seizure, at any age
- New weakness, numbness or clumsiness on one side of the body
- New loss of vision, or new double vision
- Vomiting together with headache
- Drowsiness, confusion, or difficulty waking someone
See your doctor or a neurosurgeon within a day or two for any of these:
- Function that is clearly worse than it was last week: walking, speech, vision, or thinking
- Headache that wakes you from sleep, or that is worse lying flat, coughing or straining
What to do now
What to do now if a scan has found a meningioma
- See a neurosurgeon, who decides what happens next with a meningioma. If you are not sure whether to see a neurosurgeon or a neurologist first, ask the doctor who ordered the scan
- Arrange the consult when the scan is found, because the wait for a neurosurgical clinic can be long. You can book a consultation yourself, or your doctor can refer you
- Bring the images themselves, on a disc or as films, not only the printed report
- Ask whether any older head scan exists anywhere, and bring a copy of it
- You may see me at my clinic at the Lung Center of the Philippines, Room 1101, Quezon Avenue, Quezon City, on Tuesday and Thursday from 2 PM
- For a child, my clinic is at the Philippine Children’s Medical Center (PCMC), Room 22, Quezon Avenue corner Agham Road, Diliman, Quezon City, on Wednesday from 2 PM
- If you live too far to travel, you can book an online consult with me on the consultation page
How common is a meningioma in Filipinos?
Meningioma is the most common tumor of the brain and its coverings. In the United States registry, it makes up about 2 in 5 of these tumors, and it is reported more often in women than in men. No Philippine registry measures how often meningioma occurs here, so there is no local figure to quote.
It is found most often in middle-aged and older adults. Children can develop a meningioma, but it happens far less often in childhood.
Where a meningioma sits and why that matters
Where a meningioma sits decides most practical things: which symptoms appear, how difficult an operation would be, and whether radiation is an option at all. Two tumors of the same size can behave very differently in different places. Swelling in the brain next to the tumor matters as much as the tumor itself.
The names in a report describe position. A convexity meningioma sits over the outer surface of the brain. A sphenoid wing tumor sits behind and beside the eye. Skull base tumors sit deep, close to the cranial nerves (the nerves for sight, hearing and the face), the brainstem and the nerves for balance. Seizures are much more likely when there is swelling around the tumor, and more likely when it is not at the skull base.
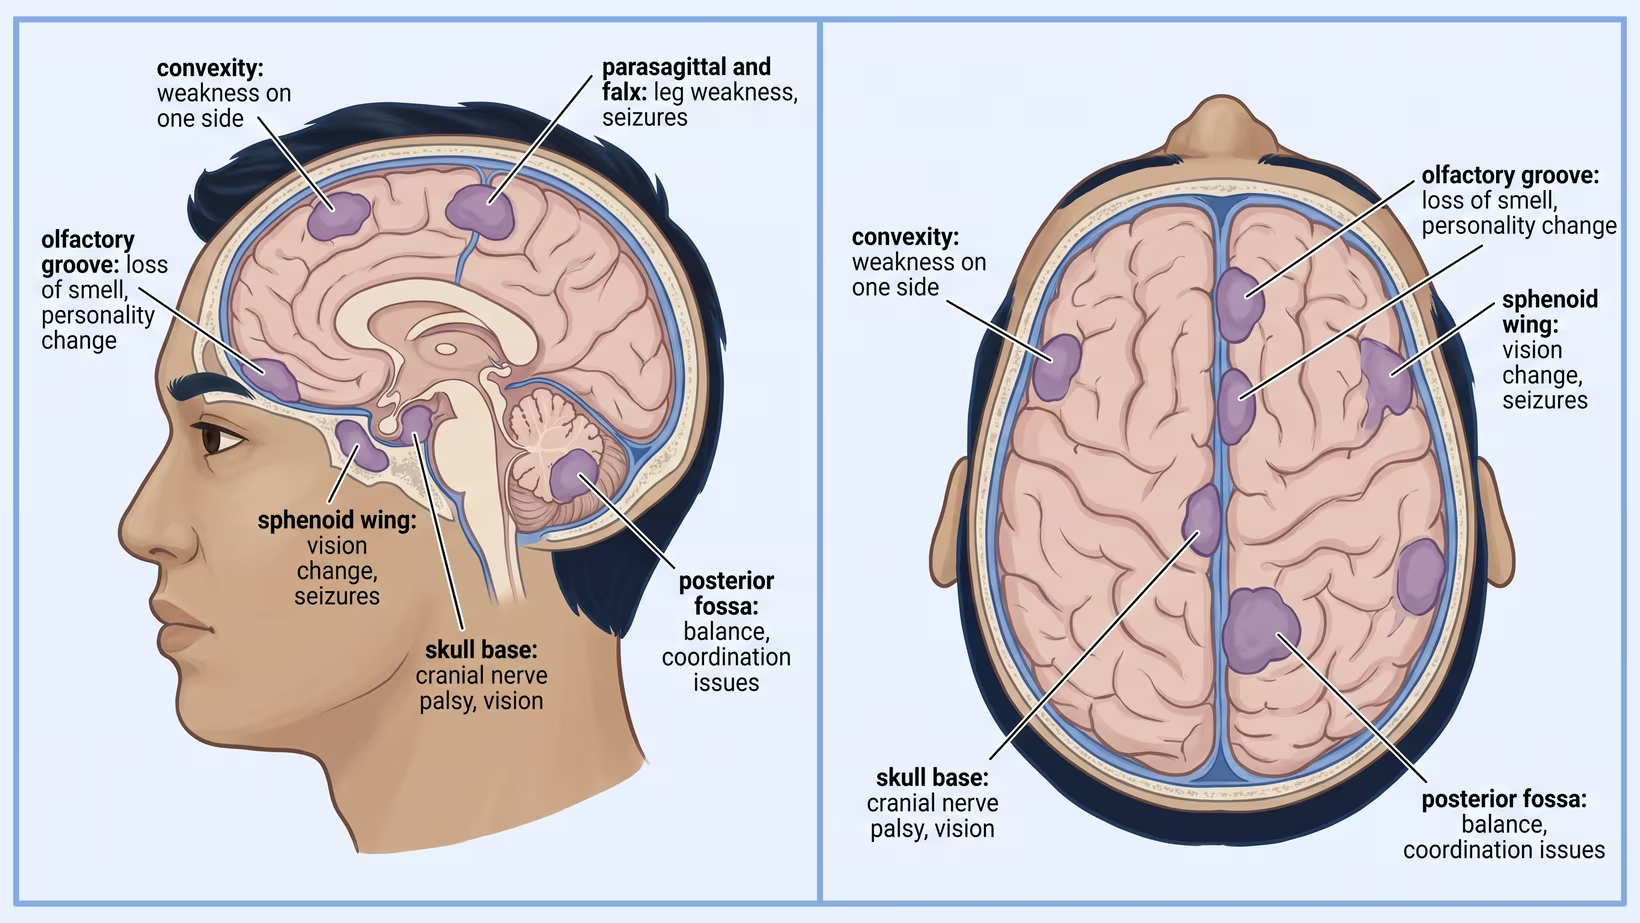
In an older adult, gradual change is worth a scan whatever the cause. It may be a chronic subdural hematoma, a slow collection of blood between the brain and its tough outer covering, rather than a tumor.
What happens after a meningioma diagnosis?
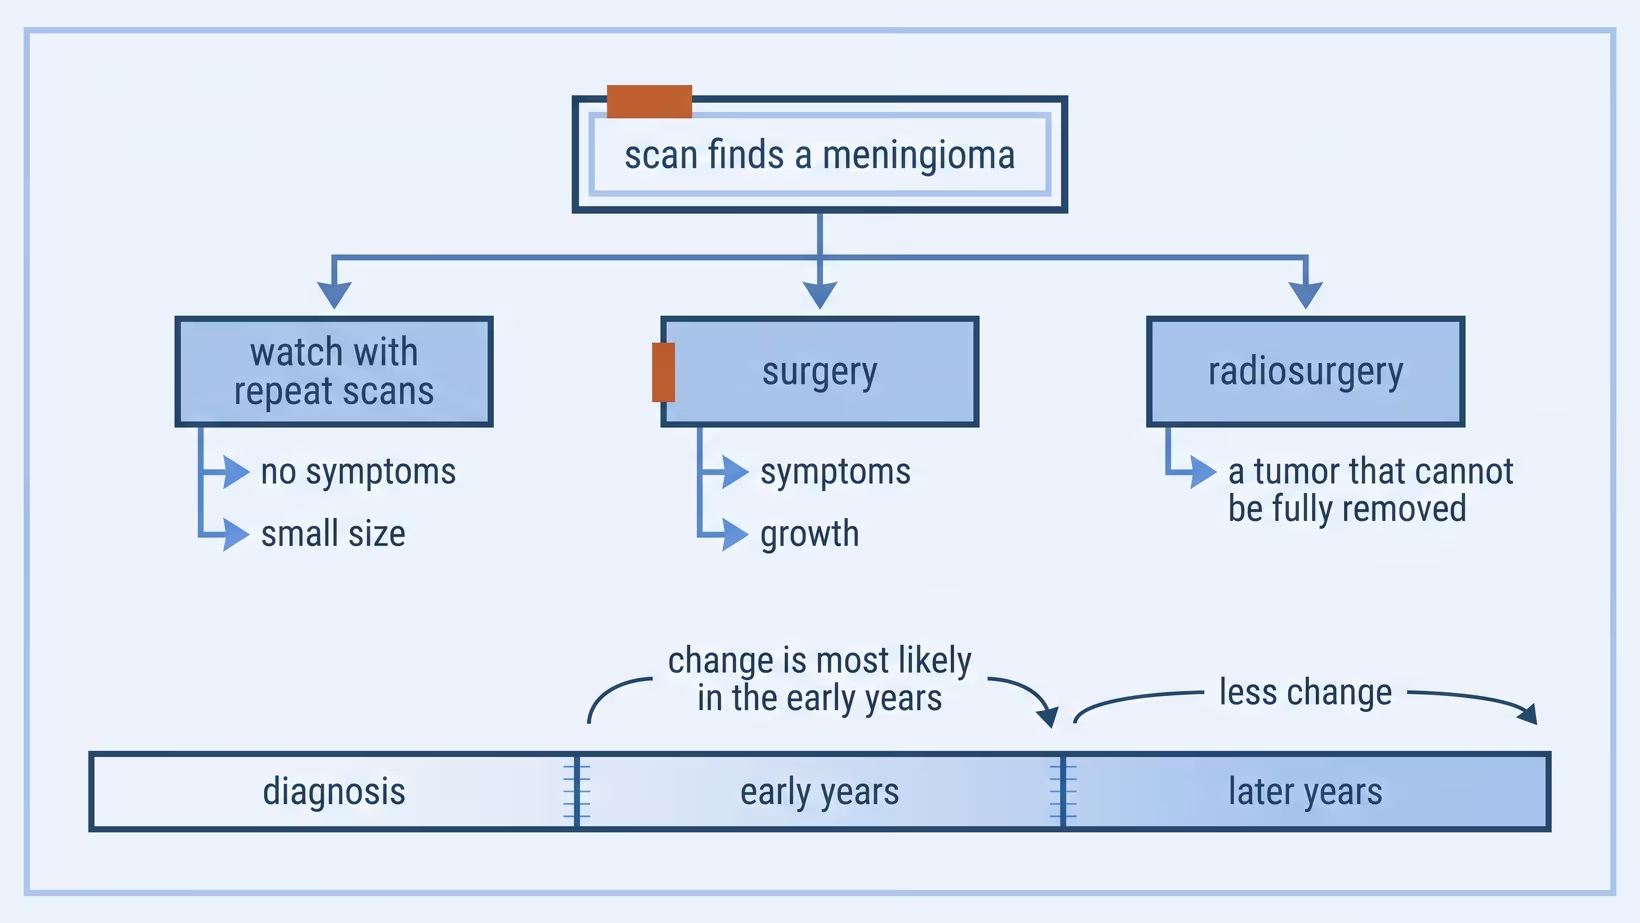
A meningioma is usually first found on MRI, a detailed scan that uses a magnet, often ordered for another reason. The images are then reviewed in clinic, and the plan follows one of three paths: watching with repeat scans, surgery, or radiosurgery, a focused dose of radiation given without opening the skull.
The choice depends on symptoms, size, exact location, swelling, growth since an earlier scan, and your age and general health. Removing the whole tumor, including the piece of covering it grew from, is the aim of surgery. When a tumor cannot be removed, or comes back and needs treatment, radiosurgery is used where the size and nearby structures allow it. Where they do not, fractionated radiotherapy, radiation given in many smaller sessions, is used.
If watching is the plan, the neurosurgeon decides how often to repeat the scan. Change is most likely in the early years, so keep every scheduled scan, especially the first few.
Does a meningioma always need surgery?
No, a meningioma does not always need surgery. Watching with repeat scans is a recognized plan, not neglect. It is used mostly when the tumor causes no symptoms, when the patient is elderly, or both. Among watched tumors found by accident, only a small number ever cause symptoms.
A surgeon is unlikely to advise watching a meningioma when it already causes symptoms, has grown since an earlier scan, has swelling around it, or is large. The same is true when it sits where a little more growth would threaten vision or another critical function.
Bring and ask
Questions to ask your doctor about a meningioma
Ask about the grade, the exact location, and whether the plan is to watch, operate or use radiation. Write these questions down before the consult, or screenshot them. A written list gets more useful answers in less time than trying to remember on the day.
- What grade is suspected, and how will that be confirmed
- Exactly where is it sitting, and what important structures are next to it
- Is there swelling in the brain around it
- Is the plan to watch, to operate, or to consider radiation, and why that one
- If we watch, when is the next scan, and what are we comparing it against
- What would make this urgent enough for me to call before that
- Who do I call at night or on a weekend
- Does anything need to change about driving, work, or being alone
For a first neurosurgery appointment, bring the actual images, every earlier scan you can find, a list of your current medicines, and one person who will remember the conversation.
What to ask about cost and PhilHealth coverage
No single cost can be given here, because it depends on the hospital, the room, the imaging and the plan. Ask the hospital billing or social service office for a written estimate. Ask the PhilHealth desk at the hospital what applies to this admission, and which documents and contributions they need from you.
Ask for the tests and the operation to be estimated separately. Ask whether the estimate includes the surgeon, the anesthesiologist, implants, intensive care, and pathology, and what happens to it if the stay is longer. Ask the surgeon’s secretary about professional fees and what is paid before admission.
The room, how much imaging is repeated, whether radiation is part of the plan, and the length of stay change the cost of meningioma surgery the most.
The referral path for a meningioma in the Philippines
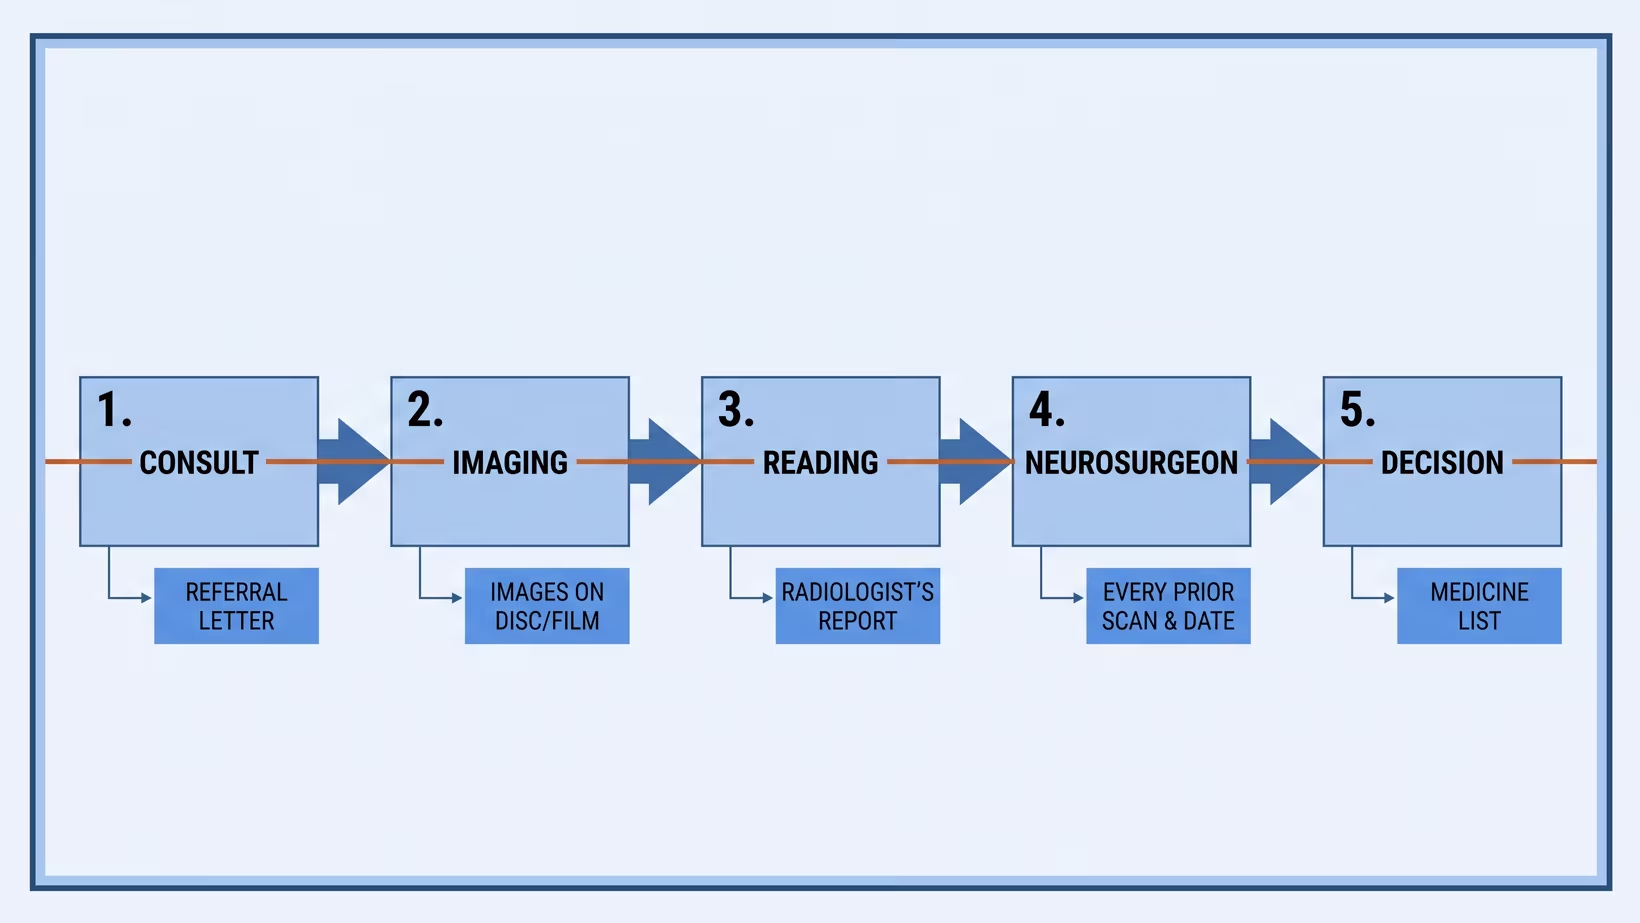
The usual route runs in one direction. The first doctor you see orders the scan, a radiologist reads it, and a neurosurgeon decides what happens next. A family physician, internist or neurologist can start this route from anywhere in the country. Arrange the first consult when the scan is found, not when symptoms change.
If you would like me to see you, my clinic days are in the box near the top of this page. If travel to Quezon City is not practical, you can have an online consult with me instead.
The wait is real. As reported in 2020, there were about 134 certified neurosurgeons in the Philippines, roughly one for every 800,000 people. They were trained in ten centers, with about three new neurosurgeons added each year.
From a province or a primary care clinic, three things help the trip. Ask your doctor for a referral letter that names the finding and the question being asked. Carry the images themselves, not only the report. Bring any older scan, even one that seemed unrelated at the time.
What should a GP do with a meningioma found on a scan?
A meningioma found by accident in a patient with no symptoms is not an emergency. It does not need treatment started in primary care. The useful work is to record a baseline examination, get the right imaging, and send a referral with enough information for the surgeon to act on.
Record a baseline neurological examination, including visual fields (side vision) and gait (how the patient walks), plus daily function and any seizure history. A later change is measured against this baseline, and nobody can reconstruct it afterwards.
The provisional diagnosis rests on MRI, not CT alone. The report helps the surgeon most when it states the size, the location, the dural attachment (where the tumor joins the dura), how close it is to the venous sinuses (the large veins inside the skull) and cranial nerves, and any swelling.
Do not start an anticonvulsant (seizure medicine) in a patient who has never had a seizure. The available evidence does not support routine preventive use, and a meningioma on its own is not a reason to start it. A patient who is already taking a seizure medicine should not stop or change it without asking the doctor who prescribed it.
Tell the patient that most of these grow slowly, the plan is a neurosurgical opinion rather than an immediate operation, and a first seizure, a drop in alertness, or sudden weakness means going to the nearest emergency room now, not waiting for the next visit.
When to refer, and what to send with the patient
Send a patient with a meningioma to the emergency room now for reduced alertness or new confusion, headache with vomiting, or a seizure from which the patient has not fully recovered. These timings assume you have examined the patient; the advice to patients above sends a first seizure or new loss of vision to the emergency room now.
Refer the same day or the next for a first seizure from which the patient has fully recovered, worsening function, or new visual loss. Refer routinely when it was found by accident and the examination is normal. Send the images and your written findings.
Send to the emergency room now:
- Reduced alertness or new confusion
- Headache with vomiting
- A patient who has not fully recovered after a seizure
Refer the same day or the next:
- A first seizure from which the patient has fully recovered
- A neurological problem (weakness, numbness or loss of function) that has progressed over days to weeks
- New visual loss, or a visual field defect on examination
- Headache worse on lying flat
Refer routinely:
- Incidental finding, no symptoms, normal examination
- Stable findings with old imaging available for comparison
- A patient who needs the plan explained more than they need an operation
Send with the patient:
- The images themselves, on disc or film, not only the radiologist’s report
- The date of every prior scan, so growth can be measured
- Your neurological findings, written down
- Seizure history, including single events years ago
- The full medicine list, naming any blood thinner (an anticoagulant or antiplatelet, which makes blood clot more slowly)
- Other illnesses (comorbidities) that would affect anesthesia
- A contact number for you that is answered
Frequently asked questions
Did something I did cause this?
In most people the cause of a meningioma is never identified. Stress, mobile phones and food have not been shown to cause it. Tell your doctor if you ever had radiation to the head or take a hormone medicine long term. Do not stop the medicine on your own; ask the doctor who prescribed it.
Can medicine shrink a meningioma?
No drug is established as a standard treatment for meningioma. Medicines are used to control symptoms such as seizures, not to remove the tumor.
Is a meningioma hereditary?
For most patients with a meningioma, no inherited cause is found. Tell your doctor if other relatives have had tumors of the brain or nerves, because a family pattern changes what a specialist looks for.
Should a healthy person get a scan to check?
No, a healthy person does not need a scan to check for a meningioma. Findings that look like a tumor do appear on brain MRI in people with no symptoms, more often with older age and with higher resolution scanners. That is not a reason to screen healthy people.
Can a child have a meningioma?
Yes, a child can have a meningioma, though far less often than an adult. It is managed by a neurosurgeon, with the plan built on the location and what the tissue shows. The specialist may also check for an inherited cause.
Can I still work or drive?
If you have had a seizure, do not drive, work at height or swim alone until your doctor tells you it is safe. Whether you can work or drive with a meningioma depends on your symptoms, especially whether you have had a seizure. It is a question for the doctor who knows your case. Ask specifically about driving, working at height, swimming alone, and night shifts.
See sources
- Goldbrunner R et al, for the European Association of Neuro-Oncology. EANO guideline on the diagnosis and management of meningiomas. Neuro-Oncology, 2021. PMID 34181733, doi:10.1093/neuonc/noab150
- Price M, Ostrom QT et al, Central Brain Tumor Registry of the United States. CBTRUS Statistical Report: Primary Brain and Other Central Nervous System Tumors Diagnosed in the United States in 2017-2021. Neuro-Oncology, 2024. PMID 39371035, doi:10.1093/neuonc/noae145
- Islim AI, Jenkinson MD et al. Incidental intracranial meningiomas: a systematic review and meta-analysis of prognostic factors and outcomes. Journal of Neuro-Oncology, 2019. PMID 30656531, doi:10.1007/s11060-019-03104-3
- Englot DJ et al. Seizures in supratentorial meningioma: a systematic review and meta-analysis. Journal of Neurosurgery, 2016. PMID 26636386, doi:10.3171/2015.4.JNS142742
- Morris Z, Al-Shahi Salman R et al. Incidental findings on brain magnetic resonance imaging: systematic review and meta-analysis. BMJ, 2009. PMID 19687093, doi:10.1136/bmj.b3016
- Louis DN, Perry A, Cree IA et al. The 2021 WHO Classification of Tumors of the Central Nervous System: a summary. Neuro-Oncology, 2021. PMID 34185076, doi:10.1093/neuonc/noab106
- Ferraris KP, Vesagas T, Seng K et al. The state of neurosurgical training and education in East Asia: analysis and strategy development for this frontier of the world. Neurosurgical Focus, 2020. PMID 32114563, doi:10.3171/2019.12.FOCUS19814
- National Institute for Health and Care Excellence. Suspected cancer: recognition and referral, section 1.9 Brain and central nervous system cancers. NICE guideline NG12, 2015. https://www.nice.org.uk/guidance/ng12
- Weill A, Nguyen P, Labidi M et al. Use of high dose cyproterone acetate and risk of intracranial meningioma in women: cohort study. BMJ, 2021. PMID 33536184, doi:10.1136/bmj.n37
- Vienne-Jumeau A, Tafani C, Ricard D. Environmental risk factors of primary brain tumors: A review. Revue Neurologique, 2019. PMID 31526552, doi:10.1016/j.neurol.2019.08.004